For decades, the standard for assessing cardiovascular health in the United States has been the routine lipid panel. Millions of Americans head to their local labs every year to have their low-density lipoprotein (LDL)—commonly referred to as "bad" cholesterol—measured. While this practice has become a cornerstone of preventative medicine, a groundbreaking new study from Northwestern Medicine suggests that our reliance on LDL may be leaving too many people at risk of preventable heart attacks and strokes.
New research, published in the journal JAMA, indicates that measuring apolipoprotein B (apoB) is a significantly more effective method for determining which patients require aggressive, life-saving interventions. According to the study, shifting our clinical focus toward apoB could not only save more lives but also prove to be a highly cost-effective strategy for the American healthcare system.
The Core Finding: A More Accurate Marker of Risk
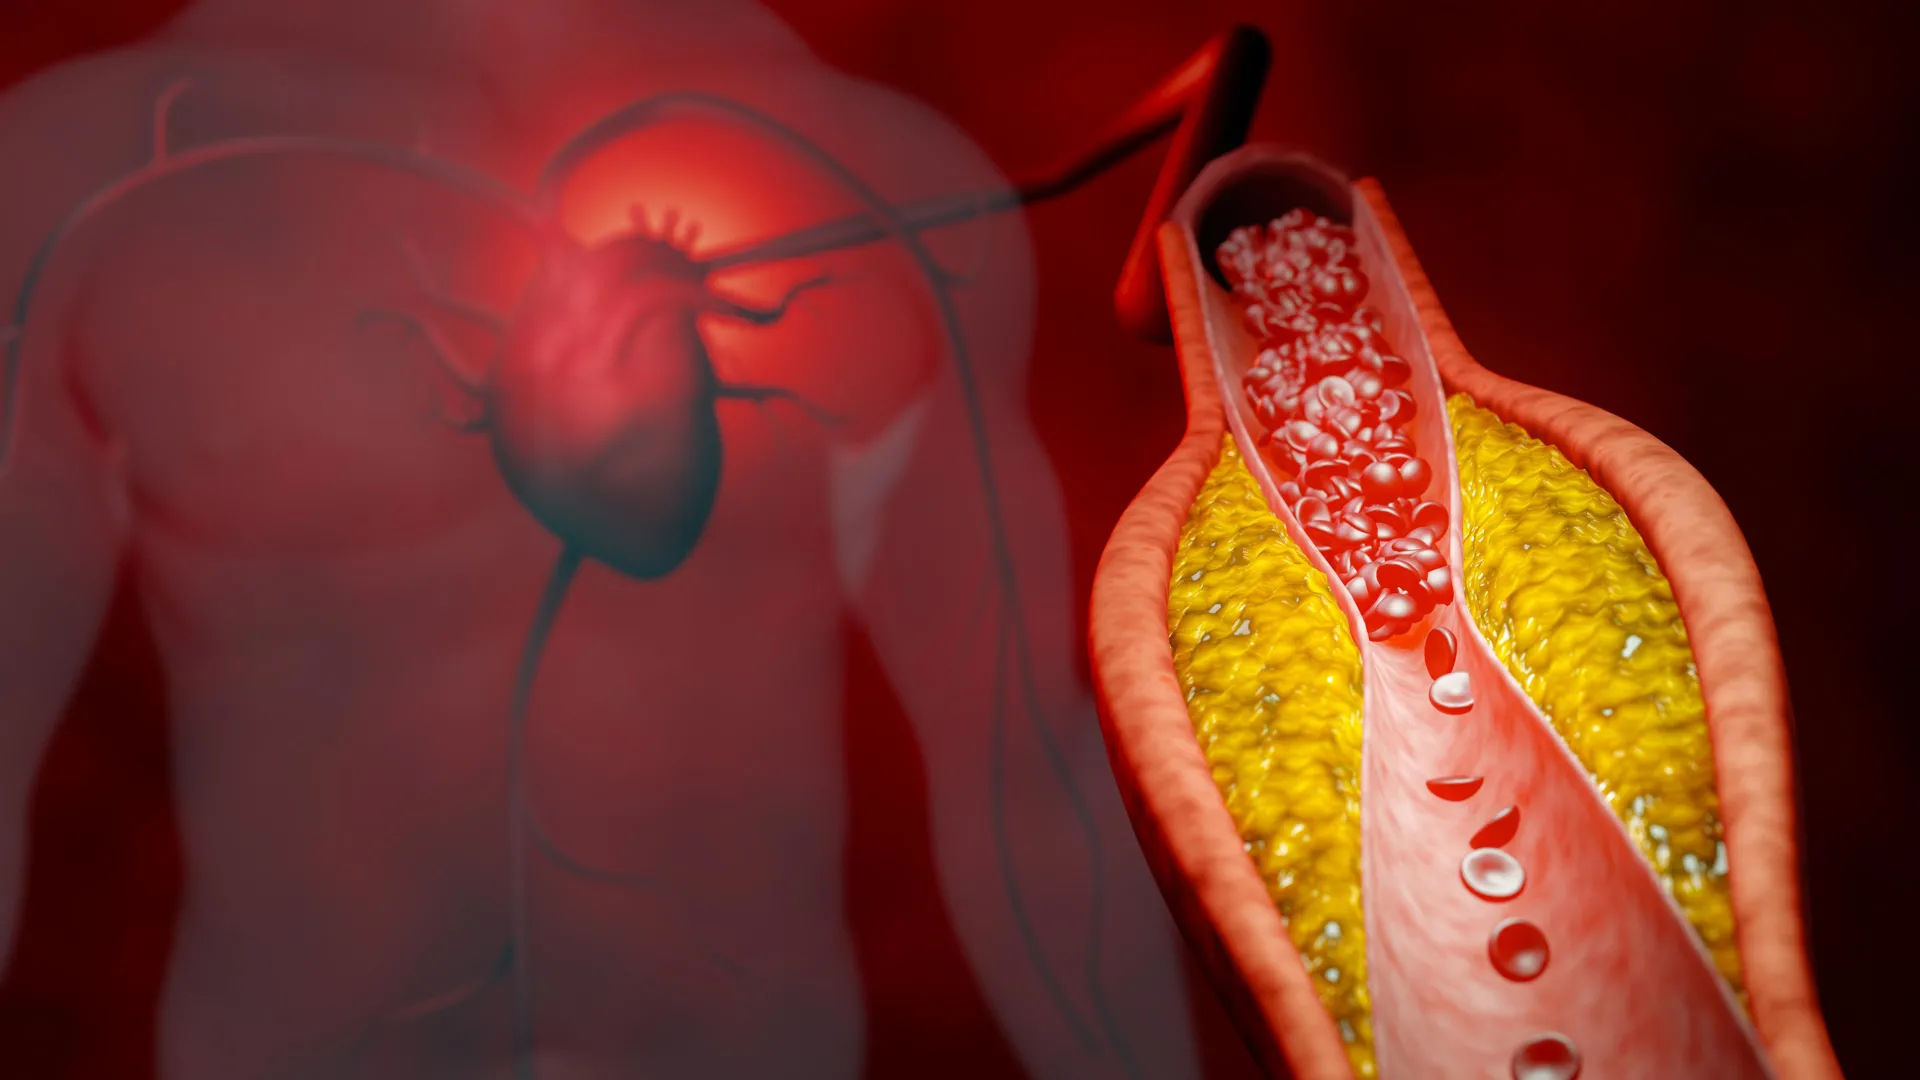
Heart disease remains the leading cause of death in the United States, accounting for an immense portion of annual healthcare expenditure. The mechanism of the disease is well-understood: tiny, cholesterol-carrying particles circulate in the bloodstream and, over time, become trapped within artery walls. Once trapped, these particles accumulate into plaques, which restrict blood flow, harden arteries, and eventually lead to catastrophic cardiovascular events like heart attacks and strokes.
For years, clinicians have utilized LDL cholesterol and non-HDL cholesterol as proxies for this risk. While these metrics provide valuable insights, they are fundamentally indirect. LDL testing measures the mass of cholesterol within these particles, but it fails to account for the total number of particles themselves.
The study from Northwestern University Feinberg School of Medicine argues that apoB is a superior clinical tool because it directly counts the number of harmful, plaque-forming particles circulating in the blood. "We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice," says lead author Ciaran Kohli-Lynch, assistant professor of preventive medicine at Northwestern. "Furthermore, these health benefits were achieved at a cost that represents good value for U.S. healthcare payers."
Chronology of a Shifting Paradigm
The debate surrounding cholesterol testing is not new, but the push for apoB has gained significant momentum in recent years. To understand why this shift is occurring now, it is helpful to look at the evolution of lipid management:
- The Era of the Standard Lipid Panel: Since the mid-20th century, the medical community has focused on total cholesterol and, later, LDL-C. These tests were affordable, easy to automate, and established the foundation for the statin revolution.
- The Rise of Non-HDL-C: As research progressed, doctors realized that non-HDL cholesterol—which includes all "bad" cholesterol particles—was a better predictor than LDL alone. Many clinical guidelines began to prioritize non-HDL as a secondary target.
- The ApoB Movement: Cardiologists and researchers began advocating for apoB, noting that because every atherogenic (plaque-forming) particle contains exactly one molecule of apoB, measuring this protein provides a near-perfect count of the particles capable of clogging arteries.
- The Current Study: Published in JAMA, the Northwestern analysis represents the first comprehensive simulation to bridge the gap between clinical efficacy and economic feasibility. By modeling a population of 250,000 U.S. adults, researchers provided the data necessary to argue that the extra cost of an apoB test is a sound investment for public health.
Supporting Data: The Power of Simulation
To validate the clinical and economic impact of switching to an apoB-centered approach, the Northwestern team utilized a sophisticated computer simulation. The model represented 250,000 U.S. adults who were eligible for statin therapy but had not yet developed clinical cardiovascular disease.
The researchers compared three primary strategies for guiding treatment:
- The LDL-C Approach: Using standard LDL levels to trigger medication adjustment.
- The Non-HDL-C Approach: Using the broader non-HDL measurement to guide therapy.
- The ApoB Approach: Using the particle-count method as the primary driver for intensifying medication.
In each scenario, if a patient failed to meet their target levels, the protocol dictated a step-up in treatment—starting with more potent statins and, if necessary, adding secondary medications like ezetimibe.
The results were compelling. The simulation followed these patient groups over their lifetimes, projecting life expectancy, quality of life, heart attack and stroke incidence, and cumulative healthcare costs. The apoB-guided strategy consistently outperformed the alternatives. It not only prevented a greater number of cardiovascular events but also resulted in a better "cost-effectiveness" ratio, suggesting that the initial investment in a more specialized test is offset by the reduction in expensive hospitalizations, surgeries, and long-term disability care.
Official Responses and Clinical Implications
The academic and clinical communities have greeted these findings with significant interest. The study comes at a pivotal moment, as the American Heart Association and 10 other medical organizations recently released updated guidelines recommending that younger populations begin cholesterol-lowering therapy earlier than previously advised.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," explains Dr. Kohli-Lynch. By identifying high-risk patients who might have "slipped through the cracks" under the LDL-only model, clinicians can provide more precise, personalized care.
The Barriers to Adoption
Despite the robust data, the apoB test is not yet a standard fixture in every primary care setting. Dr. Kohli-Lynch acknowledges that the primary obstacle is operational. Currently, measuring apoB usually requires an additional blood draw or a specialized order outside of the standard lipid panel, which increases inconvenience for the patient and requires extra administrative effort from the healthcare provider.
However, the study suggests that the "inconvenience" must be weighed against the massive burden of heart disease. If a single, slightly more complex test can identify a patient at high risk for a heart attack years before it happens, the medical community may be forced to reconsider the current workflow.
Implications for Future Care
The implications of this study reach far beyond the laboratory. If healthcare systems shift toward apoB, it could fundamentally alter how primary care physicians interact with patients regarding cardiovascular health.
1. Precision Medicine
ApoB allows for "precision lipidology." Two patients might have the same LDL level, but one could have a much higher number of small, dense particles (high apoB) while the other has fewer, larger particles (lower apoB). Under current guidelines, both might receive the same treatment, even though their actual risk profiles differ significantly. ApoB eliminates this ambiguity.
2. Economic Efficiency
Critics of adding new diagnostic tests often cite cost. However, this research demonstrates that "cost-effective" does not mean "cheap." It means that the value provided—in this case, years of life gained and expensive medical events avoided—far outweighs the price of the test. For insurance providers and healthcare systems, this is a powerful argument for changing clinical practice guidelines.
3. Patient Empowerment
When patients understand that their risk is based on the number of harmful particles in their blood, they may have a better grasp of why medication adherence is critical. It shifts the conversation from a vague, abstract number (LDL) to a concrete biological mechanism (particle count), which can improve patient engagement and adherence to therapy.
Conclusion: A Turning Point?
As we move deeper into an era of personalized medicine, the limitations of the standard lipid panel are becoming increasingly difficult to ignore. The Northwestern Medicine study serves as a wake-up call, providing the scientific evidence needed to challenge the status quo.
While transitioning to an apoB-focused screening model will require logistical adjustments and, perhaps, a shift in medical education, the potential benefits are undeniable. By moving from measuring the weight of cholesterol to counting the particles that drive heart disease, we have the potential to prevent millions of heart attacks and strokes.
For the millions of Americans navigating their cardiovascular health, this study offers a hopeful prospect: a future where the most common killer in the nation is managed not just with broader strokes, but with the precision of modern science. As Dr. Kohli-Lynch and his colleagues, including Drs. John Wilkins and Samuel Luebbe, have demonstrated, the tools to improve outcomes are already at our disposal—we simply need to change how we use them.