








September 17, 2026 | 3 min read
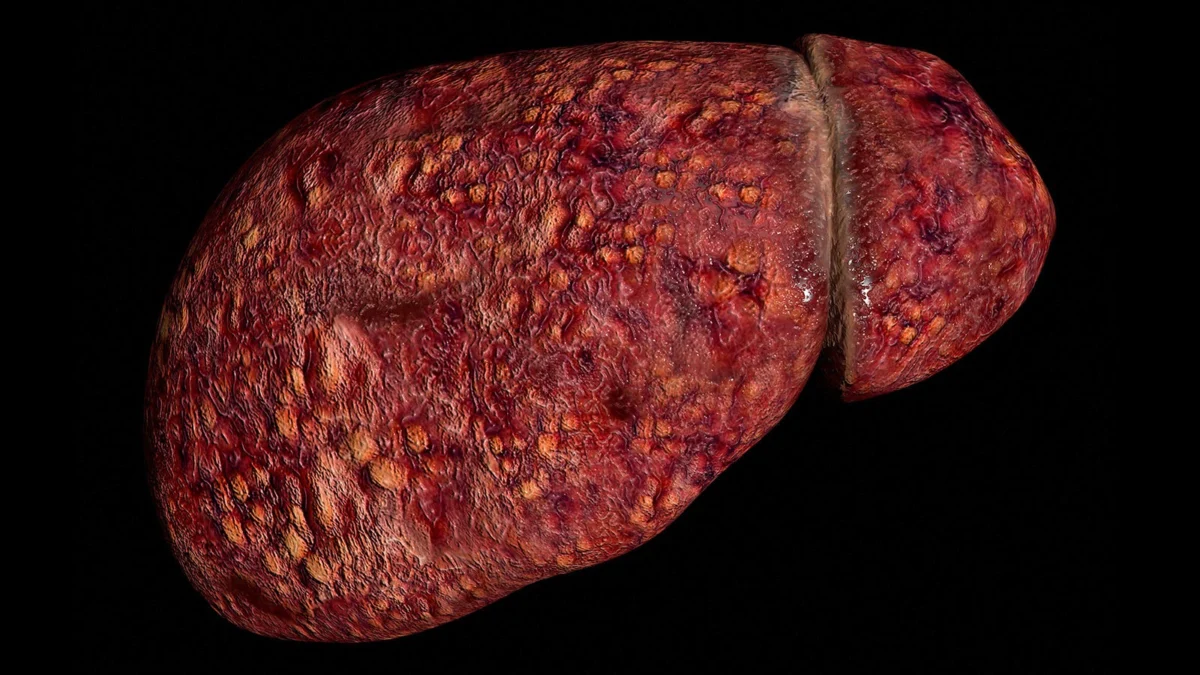
A concerning shift in the landscape of metabolic health has emerged, as new research reveals that a significant portion of patients suffering from cirrhosis linked to Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) are significantly younger than historical trends would suggest. According to a landmark prospective multicenter study published in Clinical Gastroenterology and Hepatology, one-quarter of patients presenting with advanced liver scarring (cirrhosis) are under the age of 50. This demographic is not merely experiencing the disease earlier; they are battling a distinct, high-stakes phenotype driven by a "perfect storm" of genetic susceptibility and metabolic dysfunction.
Main Facts: The New Reality of Early-Onset MASLD
The study, led by Rohit Loomba, MD, of the University of California San Diego, provides a sobering look at how MASLD—formerly known as NAFLD—is evolving. The research indicates that for younger adults, the path to cirrhosis is significantly more aggressive.
At the core of the findings is the discovery that early-onset MASLD cirrhosis is driven by a unique interplay of factors. While traditional risk factors like obesity remain relevant, the study highlights that high genetic risk scores and the presence of type 2 diabetes are the primary independent predictors of advanced liver disease in patients under 50.
The data suggests that the clinical community must move away from the assumption that liver failure is a "disease of aging." Instead, clinicians are being urged to recognize that young patients with specific genetic markers and metabolic comorbidities are at a disproportionately high risk for rapid progression to irreversible liver damage.
A Chronology of Discovery and Research
The investigation was conducted through the Nonalcoholic Steatohepatitis (NASH) Clinical Research Network, a prestigious national cohort. The journey to these findings involved a rigorous analysis of 2,395 patients, all of whom had biopsy-confirmed MASLD.
- Cohort Identification: Researchers aggregated data from 2,395 participants to observe long-term outcomes and metabolic profiles.
- Defining the "Early" Cohort: The researchers established the "early-onset" group as the lowest quartile of age, which set the threshold at less than 50 years old.
- Genetic Profiling: The team focused on three key single-nucleotide polymorphisms (SNPs)—PNPLA3, HSD17B13, and TM6SF2—which have long been implicated in liver health. By calculating a cumulative genetic risk score (ranging from 0 to 6), they were able to quantify the inherited burden each patient carried.
- Correlation Mapping: Once the cohort was defined and genetic data mapped, the team utilized multivariable models to adjust for demographic variables. This allowed them to isolate the specific impact of type 2 diabetes and genetic predisposition on the development of cirrhosis.
- Clinical Validation: The findings were finalized in 2026, culminating in the publication of the results in Clinical Gastroenterology and Hepatology, providing a new blueprint for how physicians should interpret screening results in younger patients.
Supporting Data: Quantifying the Risk
The numbers derived from the study paint a vivid picture of the risks involved. In multivariable models, the presence of type 2 diabetes emerged as a massive red flag, yielding an odds ratio (OR) of 3.74 (95% CI 2.08-6.82, P<0.001). Similarly, a high genetic risk score proved to be a powerful indicator, with an OR of 2.33 (95% CI 1.26-4.23, P=0.006).
Perhaps most striking is the synergistic effect of these variables. For patients with a low genetic risk score, the prevalence of cirrhosis was 2.0% in the absence of type 2 diabetes; this jumped to 9.5% when type 2 diabetes was present. For those with a high genetic risk score, the prevalence of cirrhosis stood at 6.2% without diabetes, climbing to 10.7% with the disease.
Furthermore, the study highlighted a significant diagnostic gap. Current screening tools, most notably the Fibrosis-4 (FIB-4) index, are heavily weighted by age. Because the FIB-4 index uses age as a variable to predict risk, it frequently underestimates fibrosis in younger populations. The study found that approximately 30% of patients with early-onset MASLD cirrhosis maintained a "normal" FIB-4 score of less than 1.3. This represents a dangerous diagnostic blind spot, as these patients are often falsely categorized as low-risk and subsequently denied the life-saving interventions they require.
Official Responses and Expert Perspective
Dr. Rohit Loomba, the study’s lead investigator, emphasized the paradigm shift this research necessitates. "Our findings show that younger adults who develop cirrhosis from MASLD are not simply experiencing the same disease earlier," Dr. Loomba stated in a recent press release. "They appear to have a unique combination of genetic susceptibility and metabolic risk factors that accelerate progression to advanced liver disease."
Co-author Veeral Ajmera, MD, also of the University of California San Diego, echoed these concerns, particularly regarding current diagnostic protocols. "Because current screening tools like FIB-4 incorporate age, they miss almost a third of patients with early-onset MASLD cirrhosis," Dr. Ajmera noted.
The researchers argue that the clinical standard should be updated immediately. The study suggests that for younger patients, a more conservative FIB-4 cut-point of 1.0 would identify 82.7% of cases, a significant improvement over the standard threshold. Both doctors advocate for a move toward direct referral for specialized fibrosis assessment in younger patients, even when standard algorithms suggest the risk is low.
Implications for Future Clinical Practice
The implications of this study are far-reaching, demanding a fundamental change in how primary care physicians and hepatologists approach metabolic health in younger patients.
1. Re-evaluating Screening Thresholds
The "age-dependent" nature of current screening tools like the FIB-4 index is clearly insufficient for the modern patient profile. Medical organizations will likely need to adopt age-stratified or age-agnostic screening protocols to ensure that high-risk individuals under 50 are not missed.
2. Genetic Literacy in Hepatology
As the influence of SNPs like PNPLA3 and TM6SF2 becomes clearer, genetic testing may transition from a research tool to a standard clinical instrument. Identifying "genetically high-risk" patients early could allow for more aggressive management, such as earlier initiation of pharmacotherapy or more frequent surveillance.
3. Targeted Interventions
The study highlights that younger patients with cirrhosis often present with distinct metabolic profiles, including higher BMIs and specific biochemical markers like lower alanine aminotransferase (ALT) levels. Future clinical trials should focus on this specific, younger population to determine if traditional weight-loss interventions or newer metabolic therapies need to be intensified for those with high genetic risk.
4. A Call for Early Detection
Ultimately, the study serves as a wake-up call. The rise of MASLD-related cirrhosis in the under-50 demographic suggests that the silent progression of liver disease is occurring much earlier than previously realized. By refining screening thresholds and incorporating genetic risk into the diagnostic workflow, the medical community can intervene before the damage reaches the point of no return.
As the researchers noted in their closing remarks, the next phase of this work must focus on validating these new, "age-aware" screening thresholds. In an era where metabolic diseases are on the rise globally, the ability to identify and protect the liver health of the next generation has become a critical pillar of preventative medicine. The transition from reactive care to proactive, risk-stratified management will be the defining challenge for the future of hepatology.







