









For decades, the medical community has grappled with a complex paradox in oncology: the very tools designed to save lives—breast cancer screening programs—can occasionally identify cancers that would never have posed a threat to a woman’s health. This phenomenon, known as "overdiagnosis," has long been a central, contentious point in public health debates. It represents a significant ethical and clinical challenge, as it can lead to unnecessary treatments, psychological distress, and physical side effects for conditions that might have remained indolent for a lifetime.
However, a groundbreaking new study involving an international team of researchers suggests that the widely cited estimates of overdiagnosis—some claiming as high as 30% to 50%—may be significantly inflated. By re-evaluating decades of randomized controlled trials (RCTs) through a more precise temporal lens, researchers have concluded that the actual rate of overdiagnosis is likely below 5%. This finding promises to reshape how we interpret screening data, guide international health policy, and communicate risks to the public.
The Core Facts: Understanding Overdiagnosis
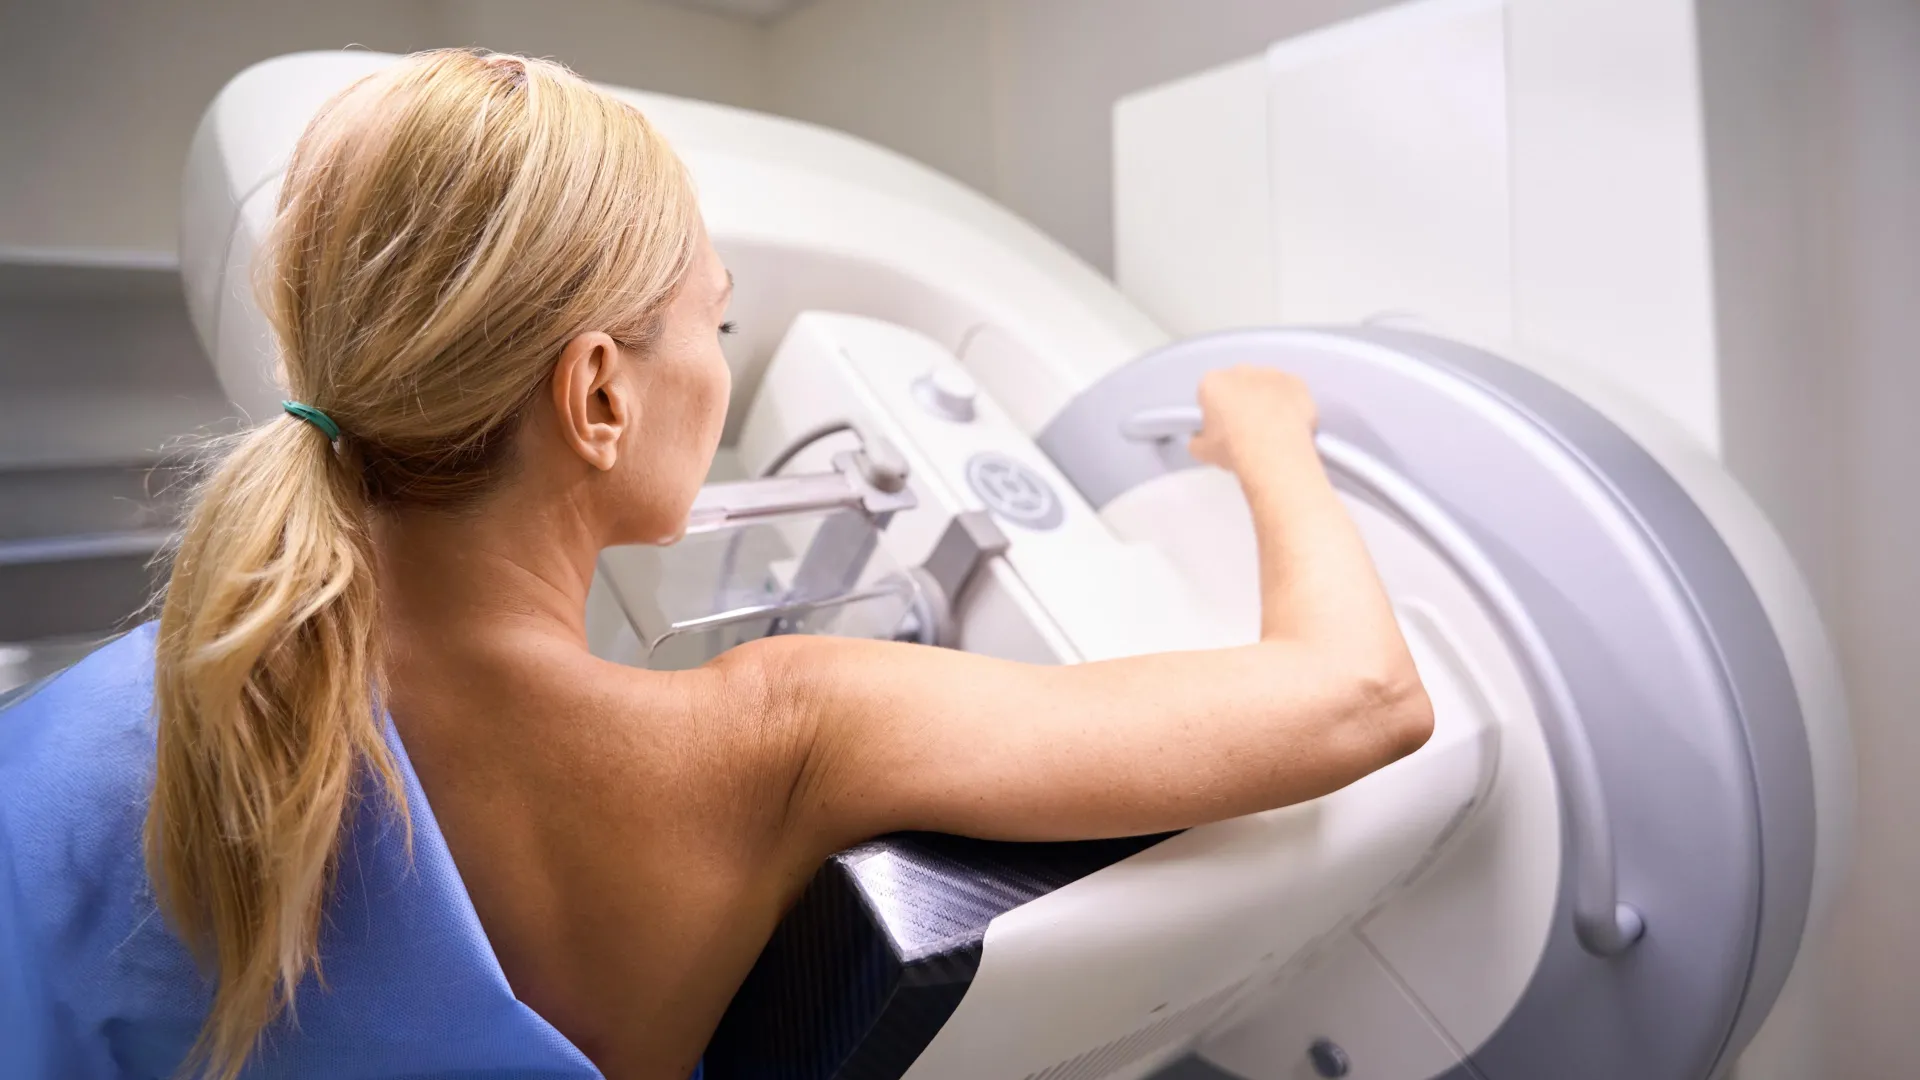
At its simplest, overdiagnosis occurs when a screening procedure, such as a mammogram, detects a cancer that would never have become symptomatic or life-threatening had it remained undetected. In such instances, the woman would have lived out her natural life without ever knowing the cancer was present, and she would have ultimately died of an entirely unrelated cause.
The definition is nuanced. It also encompasses scenarios where a patient is diagnosed with a slow-growing breast cancer but passes away from a separate, unrelated condition shortly thereafter. In these cases, the screening process may have identified a malignancy, but the intervention provides no tangible survival benefit, potentially exposing the patient to the burdens of treatment without the reward of increased life expectancy.
Historically, the specter of overdiagnosis has been used to argue against universal screening programs. If a significant percentage of detected cancers are "clinically insignificant," the argument goes, then the societal costs—both financial and human—may outweigh the benefits of early detection.
A Chronology of the Debate
The controversy over overdiagnosis is as old as organized screening itself. In the mid-20th century, as mammography began to move from a diagnostic tool for symptomatic women to a population-based screening instrument for asymptomatic women, researchers recognized that they were uncovering a broader spectrum of breast disease.
The Rise of the High Estimates
Early randomized controlled trials, conducted between the 1960s and the 1990s, were designed to determine if mammography could reduce breast cancer mortality. As the data from these trials matured, researchers began to notice an "excess" of diagnoses in the screened groups compared to the control groups. At the time, this excess was largely attributed to overdiagnosis. Because these trials were pioneering, many were conducted before modern follow-up techniques were standardized. As a result, many early analyses failed to account for the "lead time"—the period between when a cancer is detected by screening and when it would have been detected by symptoms.
The Danish Reference Point
To test the validity of these historical figures, researchers turned to Denmark. Denmark represents a unique "natural experiment" in public health. Because the country rolled out organized breast cancer screening in different regions at different times—staggered by up to 17 years—it provided a perfect dataset to observe how incidence rates changed following the introduction of screening.
By tracking the evolution of diagnoses in Danish regions, researchers observed a predictable pattern: an initial "spike" in cancer detections immediately following the launch of screening, followed by a gradual stabilization. Crucially, they found that when the data was adjusted for the natural aging of the population and the subsequent shifting of diagnosis dates, the rate of true overdiagnosis remained consistently low, hovering below 5%.
Supporting Data: Re-analyzing the Randomized Trials
The research team, led by Professor Sisse Helle Njor of the University of Southern Denmark and Lillebælt Hospital, undertook the monumental task of re-examining the eight major randomized trials that have defined the field: the New York Health Insurance Plan, Malmö, Two-County, Edinburgh, the Canadian National Breast Screening Study, Stockholm, Gothenburg, and the UK Age trial.
Why Timing is Everything
The primary error in previous high estimates, according to the researchers, was a failure to account for the temporal dynamics of cancer detection. When a screening program begins, it "pulls forward" diagnoses. A tumor that would have been discovered by a doctor in 2030 might be found by a mammogram in 2027. If the study ends in 2028, researchers look at the data and see an increase in cancer cases, concluding that the screening found "extra" cancers that would never have mattered.
However, if the study were extended, the researchers would eventually see a decline in the number of diagnoses in later years, as those cases were already accounted for in the early spike. The new analysis accounted for:
- Screening Exposure: Accounting for whether women in control groups later crossed over into screening programs.
- Follow-up Duration: Ensuring that the study period was long enough to observe the expected "dip" in incidence.
- Temporal Context: Aligning the trial data with real-world, long-term outcomes observed in regional health systems like Denmark.
By applying these rigorous adjustments, the researchers found that the high estimates of 30–50% evaporated, replaced by a much more modest figure that aligned with the observed reality of modern screening.
Official Responses and Implications
The scientific community has begun to take note of the study’s implications. By correcting the narrative around overdiagnosis, the researchers aim to provide a more stable foundation for clinical guidelines.
The Expert View
"When interpreted in their full temporal context, randomized trial data are consistent with overdiagnosis of less than five percent, rather than with estimates nearing 50%," says Matejka Rebolj, Senior Epidemiologist at Queen Mary University of London. This shift in perspective is not merely academic; it is a vital component of public health communication.
Elsebeth Lynge, professor emerita at the University of Copenhagen, emphasizes the danger of misinterpretation: "If researchers do not take these factors into account, the initial increase can be mistaken for overdiagnosis." Her team’s work suggests that much of the anxiety surrounding screening programs has been fueled by statistical artifacts rather than biological reality.
Empowering Patients
For the individual woman, the implications are profound. Choosing whether to undergo screening is a deeply personal decision. Historically, women have been warned that a significant portion of the cancers found could be "overdiagnosed," potentially leading to unnecessary surgeries, radiation, or chemotherapy.
Professor Sisse Helle Njor believes this study offers a sense of relief. "Most women will not develop breast cancer, but with this study, we can now be reassured that the benefits of detecting breast cancer early and preventing premature death will outweigh the small risk of unnecessary treatment." The goal, she notes, is not to ignore the risks of screening entirely, but to provide a "realistic framework" that helps women make informed choices based on accurate, mature data rather than outdated projections.
Looking Forward: A More Realistic Framework
The study—supported by the Novo Nordisk Foundation and Cancer Research UK—serves as a reminder that science is an iterative process. As clinical trials mature and as we develop better tools to track the long-term impact of health policies, our understanding of medical interventions must evolve.
The findings do not suggest that overdiagnosis is non-existent. It remains a reality in modern medicine, and clinicians must continue to refine diagnostic tools to distinguish between aggressive tumors and indolent ones. However, by lowering the ceiling of projected overdiagnosis, this research provides a more optimistic view of breast cancer screening programs.
As health systems worldwide look to update their screening invitations and public information campaigns, they now have a more robust evidence base. By replacing the fear of high overdiagnosis rates with a clearer, evidence-backed perspective, health authorities can better fulfill their primary objective: ensuring that women have access to life-saving early detection while minimizing the harms of medical over-intervention.
In the final analysis, the evidence suggests that the balance of risks and benefits is more favorable than previously understood, reinforcing the importance of consistent screening participation in the ongoing fight against breast cancer mortality.