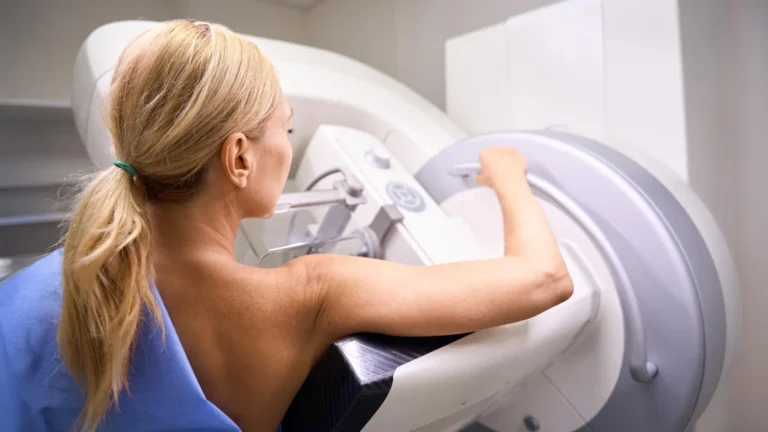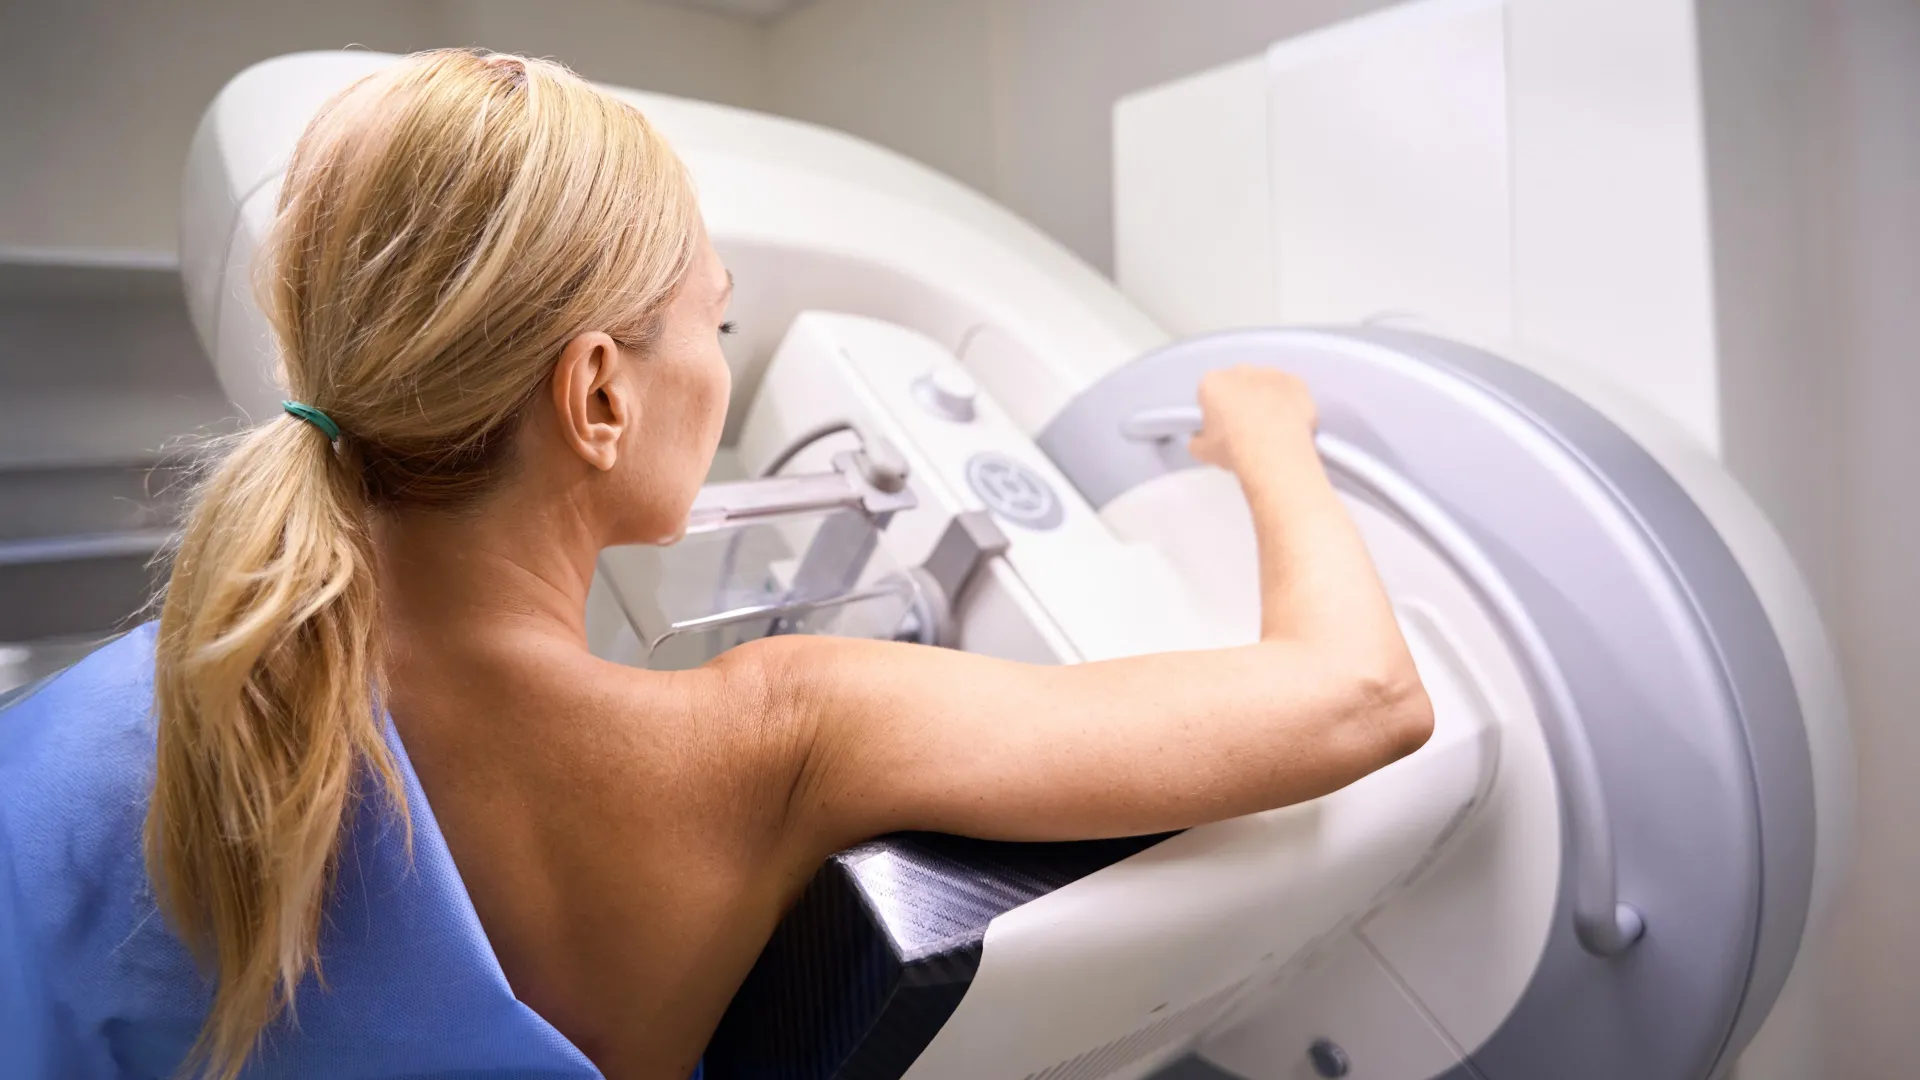
For decades, the medical community and the public have been caught in a complex, often confusing debate regarding the efficacy and risks of breast cancer screening. At the heart of this controversy is a phenomenon known as "overdiagnosis"—the detection of breast cancers that, had they been left undiscovered, would never have caused symptoms or threatened a woman’s health during her lifetime. For years, alarmist figures suggesting that 30% to 50% of screen-detected cancers fall into this category have circulated, influencing international public health policies and causing significant anxiety for women considering mammography.
However, a landmark new study led by an international team of researchers suggests that these high estimates may be based on a misunderstanding of how screening data matures over time. By reanalyzing all eight major randomized controlled trials (RCTs) and comparing them against real-world data from Denmark, researchers have concluded that the actual rate of overdiagnosis is likely below 5%—a fraction of the previously cited statistics.
Understanding the Core Conflict: What is Overdiagnosis?
To understand the weight of this new study, one must first define the clinical challenge. Overdiagnosis occurs when a mammogram identifies a tumor that is biologically indolent—meaning it is so slow-growing or non-aggressive that the patient would have lived a full life without ever knowing the cancer existed.
The definition also encompasses cases where a woman is diagnosed with breast cancer but ultimately dies from an unrelated cause shortly thereafter. In such scenarios, the screening process may have identified a lesion that was destined to be irrelevant to the patient’s longevity. While the intent of screening is to catch aggressive, life-threatening cancers at a curable stage, the incidental discovery of these "harmless" lesions can lead to unnecessary psychological distress, invasive biopsies, and aggressive treatments like surgery, radiation, or chemotherapy. The challenge for public health officials has always been to balance the life-saving benefits of early detection against these potential harms.
A Chronology of the Screening Controversy
The debate over screening efficacy has spanned half a century. In the late 20th century, the introduction of mammography was hailed as a revolutionary tool for reducing breast cancer mortality. As population-based screening programs were rolled out globally, epidemiologists began to notice a significant "spike" in cancer incidence rates shortly after the introduction of screening in specific regions.
Early Trial Interpretations
In the early days of screening research, the data from randomized trials was limited. Researchers observed a higher number of breast cancer cases in screened groups compared to non-screened control groups. At the time, many interpreted this initial surge as a sign that screening was picking up "extra" cancers—many of which were assumed to be the indolent, overdiagnosed cases mentioned above.
The Evolution of Data
As the decades passed, the "long-term" data from these trials began to paint a different picture. Epidemiologists like Elsebeth Lynge, Professor Emerita at the University of Copenhagen, have long argued that the initial rise in diagnoses is a natural, expected artifact of screening. "When screening is introduced, the number of breast cancer diagnoses initially rises because cancers are detected earlier than they would have been without screening," Lynge explains. "Over time, this should be followed by a drop, as some of these cancers would otherwise have been diagnosed later."
The failure to account for this temporal shift—and the fact that many women in control groups eventually opted for screening outside the study—led to the inflated estimates of 30–50% that have dominated the conversation for years.
Methodology: Reassessing the Global Evidence
The research team, led by Sisse Helle Njor of the University of Southern Denmark and Lillebælt Hospital, sought to rectify these historical inaccuracies. They performed a comprehensive reanalysis of eight definitive randomized trials, including the New York Health Insurance Plan, the Malmö trials, the Two-County study, the Edinburgh study, the Canadian National Breast Screening Study, and the Stockholm, Gothenburg, and UK Age trials.
The Danish Reference Model
To create a "real-world" benchmark, the team utilized data from Denmark. Denmark serves as an ideal clinical laboratory because its organized breast cancer screening program was introduced in different regions at different times, with a 17-year gap between the earliest and latest rollouts. This staggered implementation allowed researchers to track how diagnosis rates fluctuated immediately following the introduction of screening and how they stabilized over two decades.
By comparing the patterns seen in these randomized trials with the long-term, matured data from the Danish screening programs, the researchers were able to identify where the "overdiagnosis" estimates went wrong. When they applied the same temporal context to the randomized trial data, the high-percentage figures vanished, replaced by a much lower estimate of less than 5%.
Implications for Public Health and Clinical Practice
The findings of this study have profound implications for how healthcare providers communicate the risks and benefits of screening to patients.
Empowering Patient Decision-Making
For many women, the fear of "overtreatment" is a primary reason for hesitation regarding routine mammography. If women are informed that the risk of overdiagnosis is under 5%—rather than 50%—the value proposition of screening becomes much clearer.
"Most women will not develop breast cancer," says Sisse Helle Njor. "But with this study, we can now be reassured that the benefits of detecting breast cancer early and preventing premature death will outweigh the small risk of unnecessary treatment."
Informing Policy and Guidelines
International organizations that set screening guidelines often rely on meta-analyses to determine the age ranges and frequencies of recommended mammograms. The previous, inflated estimates of overdiagnosis likely led to overly cautious guidelines that may have inadvertently discouraged participation. This new study provides a more stable, evidence-based framework for policymakers to evaluate the trade-offs of screening programs. By clearing the "statistical fog," public health agencies can now focus on optimizing the detection of lethal cancers while minimizing the impact of false positives or minor, irrelevant findings.
Official Responses and Scientific Context
The study has been received as a necessary "course correction" in the field of breast cancer epidemiology. By focusing on the maturity of trial data, the researchers have highlighted a common pitfall in longitudinal studies: the tendency to draw conclusions from data before the full life cycle of a cohort has been observed.
Matejka Rebolj, Senior Epidemiologist at Queen Mary University of London, notes that previous estimates were influenced by data that had not yet reached its full temporal maturity. "When interpreted in their full temporal context, randomized trial data are consistent with overdiagnosis of less than five percent, rather than with estimates nearing 50%," she asserts.
The study has also drawn praise for its transparency. By explicitly examining three factors—the timing of the initial screening surge, the subsequent decline in later diagnoses, and the contamination of control groups—the researchers have provided a reproducible model for future epidemiological studies.
Conclusion: A Shift in Perspective
The long-standing debate over breast cancer overdiagnosis has been characterized by high-stakes figures that often caused more confusion than clarity. By rigorously re-examining the foundational randomized trials and correcting for the natural temporal shifts inherent in screening programs, the research team at the University of Southern Denmark and their colleagues have provided a significant service to women’s health.
The reality of medicine is rarely black and white, and screening for any disease will always carry the risk of incidental findings. However, with an updated understanding of overdiagnosis—shifting the estimate from an alarming 50% down to a manageable 5%—the medical community is better equipped to guide patients. This research serves as a reminder that in epidemiology, as in medicine itself, the context of time is everything. As we move forward, this evidence-based perspective will be instrumental in ensuring that breast cancer screening remains a pillar of preventive care, empowering women to make informed decisions that prioritize their health and longevity.
Funding Disclosure: This research was made possible through the support of the Novo Nordisk Foundation (Reference: NNF22OC0076184) for Casper Urth Pedersen, and Cancer Research UK (Reference: C8162/A29083) for the work of Matejka Rebolj.