





Featured Buzz – January 11, 2026
The landscape of respiratory medicine is undergoing a profound transformation. As clinical demand for faster, more accurate diagnostics grows, researchers are turning toward the synergy of Artificial Intelligence (AI) and non-invasive imaging to bridge the gap between initial screening and definitive diagnosis. Recent studies published in top-tier medical journals highlight three major breakthroughs: using ECGs to detect chronic obstructive pulmonary disease (COPD), leveraging lung ultrasound (LUS) to guide extubation in neonates, and deploying large language models (LLMs) to curb antibiotic misuse in intensive care units.
I. AI-Enhanced ECGs: A New Horizon for COPD Screening
The Clinical Challenge
Chronic Obstructive Pulmonary Disease (COPD) remains one of the world’s leading causes of mortality and morbidity. Frequently underdiagnosed until the disease is in advanced stages, patients often miss the critical window where lifestyle interventions and early therapies can significantly alter the disease trajectory. While spirometry remains the "gold standard" for diagnosis, it is rarely performed as a routine screening tool in primary care settings.
Research and Methodology
A team of investigators from the Mount Sinai Health System recently explored whether the ubiquity of the electrocardiogram (ECG)—a staple of routine cardiac checkups—could serve a dual purpose. By harnessing the computational power of a Convolutional Neural Network (CNN), researchers sought to determine if subtle, machine-readable patterns in electrical heart activity could signal the presence of underlying obstructive lung disease.
The study was massive in scale, utilizing a dataset of 208,231 ECGs from 18,225 patients with confirmed COPD, compared against a control group of 59,356 individuals matched for age, sex, and race. By training the AI model on these vast datasets, researchers aimed to identify the "digital signature" of COPD within the heart’s electrical trace.
Implications for Practice
While the researchers are careful to emphasize that ECG interpretation will never replace spirometry, they propose a paradigm shift in preventative care. "Earlier recognition may facilitate timely smoking cessation, targeted therapies, and pulmonary rehabilitation," the authors noted in eBioMedicine. By integrating AI-driven ECG analysis into existing clinical workflows, healthcare systems could flag high-risk patients for follow-up spirometry long before they present with acute respiratory failure.
II. Lung Ultrasound: Precision Extubation for VLBW Infants
The Neonatal Critical Care Dilemma
For very low birth weight (VLBW) infants, the transition from mechanical ventilation to independent breathing is a high-stakes event. Failed extubation—the inability of an infant to sustain spontaneous breathing after the ventilator is removed—is associated with increased morbidity, prolonged hospital stays, and higher healthcare costs. Historically, clinical decision-making regarding extubation has relied on subjective assessments and blood gas analysis, which lack the granular detail required for optimal timing.
Chronology of the University of Chicago Study
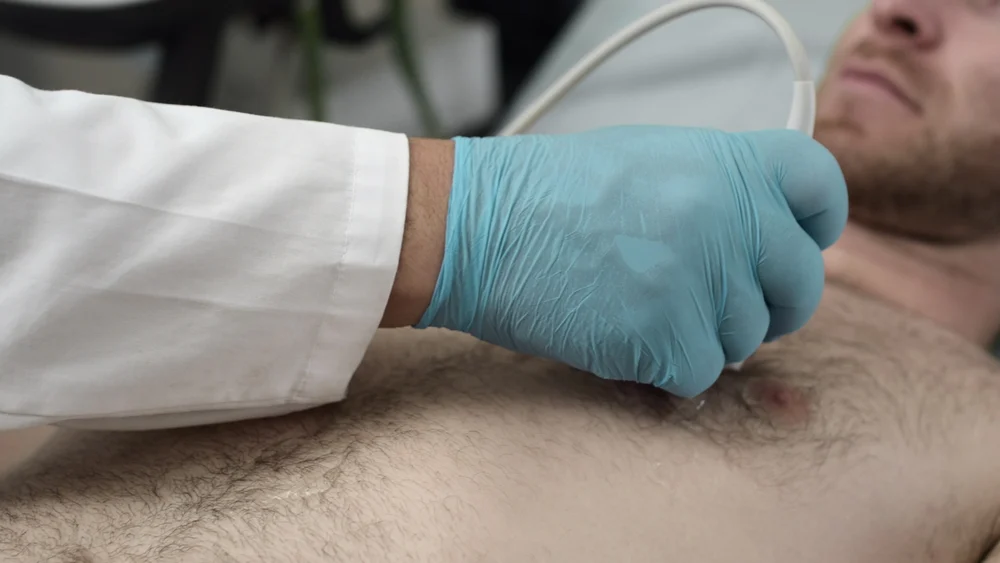
Researchers at the University of Chicago undertook a prospective study to determine if a neonatal-adapted lung ultrasound (LUS) score could provide a more reliable metric. The study monitored 45 VLBW infants who had been intubated for respiratory distress syndrome (RDS). Across the cohort, 53 extubation attempts were performed.
The methodology was precise: a lung ultrasound was conducted three to six hours prior to each attempt. The team defined a "failed extubation" as any instance where reintubation was required within seven days.
Data and Findings
The study revealed a compelling correlation between LUS scores and successful outcomes. Infants with lower, healthier LUS scores showed a significantly higher rate of extubation success compared to those with elevated scores, which typically indicate fluid accumulation, atelectasis, or poor lung aeration. Furthermore, the study clarified the role of common pharmaceutical interventions, finding that dexamethasone treatment did not necessarily correlate with improved LUS scores, suggesting that the ultrasound itself is the superior prognostic tool.
Published in the Journal of Perinatology, these findings suggest that LUS could become a routine, bedside "gatekeeper" for neonatal respiratory management, allowing clinicians to wait for the optimal biological window before attempting to extubate.
III. AI and Biomarkers: Combating Antibiotic Overuse in the ICU
The Problem of Inappropriate Antibiotic Use
In the Intensive Care Unit (ICU), differentiating between a true bacterial lower respiratory tract infection (LRTI) and non-infectious lung inflammation is notoriously difficult. This ambiguity frequently leads to the "over-prescription" of broad-spectrum antibiotics, fueling the global crisis of antimicrobial resistance (AMR) and causing unnecessary side effects for critically ill patients.
A Multimodal Diagnostic Approach
Researchers at the University of California, San Francisco (UCSF), have developed a novel diagnostic model that combines biology with silicon. The strategy hinges on the biomarker FABP4—a protein found in lung fluid that plays a role in tempering inflammation. Notably, FABP4 expression is suppressed in the presence of bacterial infection.
By combining FABP4 data with a generative AI analysis of electronic medical records (EMR), including radiological chest X-ray reports and clinician notes, the team created a robust diagnostic model. This model is designed to be accessible, functional on any HIPAA-compliant GPT-4 interface.
Performance and Official Perspectives
In an observational study of critically ill adults, the model achieved a 96% diagnostic accuracy rate, consistently outperforming the diagnostic intuition of ICU clinicians.
"This study suggests that integrating a host biomarker with large language model analysis can improve LRTI diagnosis in critically ill adults," the authors stated. The implications are staggering: the study indicates that had the model been used, it could have reduced the use of inappropriate antibiotics by more than 80%.
The UCSF team is currently moving toward the validation phase, seeking to establish this tool as a formal clinical test. Beyond LRTIs, they are already exploring how to apply this multimodal "biomarker + AI" framework to the complex, time-sensitive diagnosis of sepsis. The study, published in Nature Communications, represents a landmark step in precision medicine.
IV. Synthesis and Future Directions
The common thread linking these three studies is the shift from human-only diagnosis to "augmented intelligence."
- Efficiency: AI models are analyzing data that humans either overlook or lack the time to process (as seen in the Mount Sinai ECG study).
- Objectivity: Imaging and biomarkers are replacing subjective "clinical gut feelings" with quantifiable scores (the LUS neonatal study).
- Judicious Resource Use: The UCSF study demonstrates how AI can synthesize disparate data points to prevent systemic waste, such as the overuse of life-saving but potentially harmful antibiotics.
Challenges Ahead
Despite the promise, significant hurdles remain. Integrating these models into Electronic Health Record (EHR) systems requires rigorous cybersecurity, standardization across different hospital networks, and the careful management of "black box" algorithms. Regulatory bodies, including the FDA, will likely require ongoing longitudinal studies to ensure that these AI tools remain accurate as populations change and as new variants of respiratory diseases emerge.
Conclusion
As we enter 2026, the integration of AI into respiratory medicine is no longer a theoretical exercise. From the primary care office to the neonatal ward and the high-acuity ICU, these technologies are proving that the future of diagnostic medicine lies in the synthesis of human clinical expertise and machine-learning precision. By catching COPD earlier, timing neonatal care more accurately, and reserving antibiotics for those who truly need them, the medical community is moving toward a more sustainable and effective healthcare paradigm.
For clinicians on the front lines, these tools offer not a replacement for their expertise, but a powerful new set of eyes, capable of seeing patterns in the data that were previously invisible. As these studies move from the pages of eBioMedicine, Journal of Perinatology, and Nature Communications into the clinical mainstream, the patients stand to be the ultimate beneficiaries of this technological renaissance.