









Featured Buzz – January 11, 2026
The landscape of respiratory medicine is undergoing a profound transformation as researchers integrate artificial intelligence (AI) and novel diagnostic imaging techniques into routine clinical practice. Recent studies published in leading medical journals, including eBioMedicine, the Journal of Perinatology, and Nature Communications, highlight three critical breakthroughs: using ECGs to detect chronic obstructive pulmonary disease (COPD), employing lung ultrasound to predict extubation success in neonates, and utilizing generative AI to curb antibiotic overuse in critically ill patients.
1. ECGs as a Novel Screening Tool for COPD
Chronic Obstructive Pulmonary Disease (COPD) remains one of the world’s leading causes of mortality and morbidity, yet it is notoriously underdiagnosed in its early stages. Traditionally, diagnosis relies on spirometry—a test that is often unavailable in primary care settings or omitted during routine visits.
The Methodology
Researchers from the Mount Sinai Health System in New York sought to leverage the ubiquity of the electrocardiogram (ECG) to address this diagnostic gap. By analyzing a massive dataset of 208,231 ECGs from 18,225 patients with confirmed COPD, matched against 552,771 ECGs from 59,356 control subjects, the team trained a Convolutional Neural Network (CNN). The AI model was specifically engineered to identify subtle electrical markers in the heart that correlate with the structural and functional changes in the lungs caused by COPD.
Implications and Clinical Outlook
While the study authors emphasize that AI-enhanced ECGs are not intended to replace the gold-standard spirometry, they offer a highly pragmatic screening modality. "Earlier recognition may facilitate timely smoking cessation, targeted therapies, and pulmonary rehabilitation," the authors noted in eBioMedicine. By integrating this analysis into existing electronic health record systems, clinicians could flag "at-risk" patients during routine heart screenings, potentially slowing disease progression and alleviating the long-term healthcare burden associated with advanced lung failure.
2. Lung Ultrasound: A New Standard for VLBW Infants
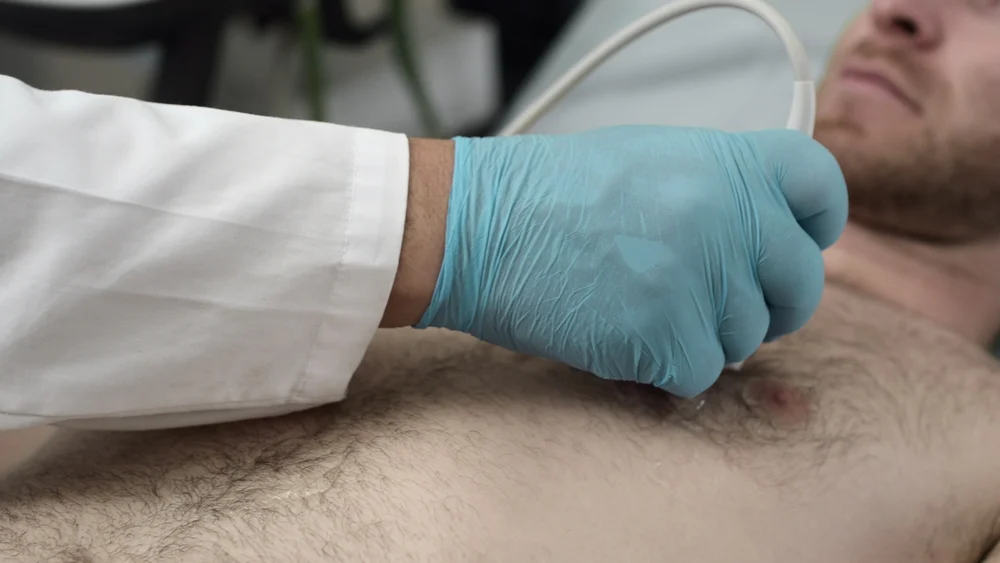
The management of Very Low Birth Weight (VLBW) infants in the Neonatal Intensive Care Unit (NICU) presents a delicate balance between respiratory support and the risks associated with prolonged mechanical ventilation. A pivotal study from the University of Chicago, published in the Journal of Perinatology, suggests that lung ultrasound (LUS) could be the key to improving extubation outcomes.
Chronology of the Research
The study observed 45 VLBW infants who had been intubated for Respiratory Distress Syndrome (RDS). Over the course of their care, 53 extubation attempts were recorded. Researchers performed lung ultrasounds three to six hours prior to each attempt, assigning scores based on a neonatal-adapted LUS protocol. The goal was to identify if specific sonographic markers could accurately predict whether an infant would successfully breathe on their own or require reintubation within a seven-day window.
Key Findings and Expert Consensus
The data revealed that LUS scores are highly predictive of extubation success when performed on the day of the procedure. Furthermore, the study dispelled common assumptions regarding pharmacological adjuncts, finding that dexamethasone treatment did not significantly correlate with lower LUS scores. This research provides neonatologists with a non-invasive, radiation-free tool to make more confident, evidence-based decisions regarding the removal of mechanical support, ultimately reducing the time infants spend on ventilators.
3. Combating Antibiotic Overuse with AI and Biomarkers
Perhaps the most ambitious project among recent breakthroughs is the diagnostic strategy developed at the University of California, San Francisco (UCSF), aimed at managing Lower Respiratory Tract Infections (LRTIs) in critically ill patients.
The Synthesis of Biology and AI
The UCSF team developed a dual-pronged diagnostic model that combines host biology with generative AI. The biological component focuses on the gene FABP4, found in lung fluid samples, which serves as a biomarker for inflammation; its expression is markedly lower in infected lung cells compared to healthy ones. This biological data is fed into a generative AI model that simultaneously analyzes the patient’s electronic medical record (EMR), including chest X-ray reports and physician clinical notes.
Supporting Data and Performance
In an observational study of critically ill adults, the model achieved a 96% accuracy rate in diagnosing LRTIs, significantly outperforming human clinicians. The implications for antibiotic stewardship are profound. The study suggests that if this tool had been implemented, inappropriate antibiotic prescriptions could have been reduced by more than 80%. Given the rising threat of antibiotic-resistant bacteria in ICU settings, this model—designed to be accessible via a HIPAA-compliant GPT-4 interface—represents a major leap forward in precision medicine.
Official Responses and Strategic Implications
The medical community is reacting with cautious optimism to these developments. Experts note that while the performance metrics of these AI models are impressive, the "human-in-the-loop" approach remains essential.
Integrating Technology into Clinical Workflow
The researchers behind these studies have been clear: these technologies are designed to augment, not replace, clinical expertise. In the case of the UCSF study, the research team is currently moving toward validating the model for widespread clinical use. Their roadmap includes:
- Clinical Trials: Ensuring the model’s performance holds up across diverse hospital systems.
- Scalability: Testing the integration of the AI interface into standard ICU workflows.
- Expansion: The team is already looking toward applying the same host-biomarker and LLM-analysis methodology to the early detection of sepsis—a condition where every hour of delay increases mortality risk.
Addressing Health Equity
A vital component of the Mount Sinai study was the careful matching of cohorts by age, sex, and race. This underscores a growing trend in medical research: the commitment to ensuring that AI models are trained on representative datasets to prevent algorithmic bias. As these diagnostic tools transition from academic research to clinical application, the focus will shift toward ensuring they are available in resource-limited settings, not just elite research hospitals.
Synthesis: A New Era of Respiratory Care
When looking at these three advancements collectively, a clear pattern emerges. We are moving away from reactive medicine—where a condition is treated only after it manifests clear, often late-stage symptoms—toward a model of predictive and precision medicine.
- ECGs for COPD represent a shift toward "opportunistic screening," utilizing existing data to find hidden disease.
- Lung Ultrasound for Neonates demonstrates the power of "point-of-care" imaging to refine high-stakes decision-making in real-time.
- AI for LRTIs showcases the potential for "augmented intelligence" to curb systemic problems, such as the overuse of antibiotics, which has plagued healthcare for decades.
Challenges Ahead
Despite the promise, significant hurdles remain. Legal and ethical frameworks regarding AI in healthcare, the necessity of rigorous data privacy, and the training requirements for clinicians to effectively interpret AI-generated insights are all works in progress. Furthermore, the reliance on proprietary models—such as the GPT-4 interface mentioned by the UCSF team—raises questions about long-term software costs and vendor dependency in hospital systems.
Conclusion
As we move further into 2026, the integration of these technologies into the daily life of hospitals seems inevitable. The ability to diagnose COPD with a routine heart check, predict respiratory success in the most vulnerable infants with ultrasound, and stop the misuse of antibiotics through AI-driven analysis of patient notes represents a significant advancement in patient safety.
For clinicians, the mandate is clear: embrace the tools that offer higher diagnostic accuracy while maintaining the fundamental human commitment to bedside care. As the studies in eBioMedicine, the Journal of Perinatology, and Nature Communications demonstrate, the synergy between human expertise and machine intelligence is the most promising frontier in modern medicine.
The future of respiratory diagnostics is not just faster or more accurate; it is proactive, personalized, and increasingly capable of saving lives before a condition reaches a critical tipping point.







