






By [Your Name/Journalistic Staff], based on insights from David E. McCarty, MD, FAASM
In the modern landscape of sleep medicine, clinicians are increasingly relying on a catch-all term to describe the frustrating persistence of insomnia in patients who appear, on paper, to be successfully treated: "hyperarousal." While this term provides a convenient shorthand for the physiologic, cognitive, and emotional activation that prevents sleep, it risks becoming a clinical dead end. As Dr. David E. McCarty, a leading expert in the field, argues, labeling a patient as "hyperaroused" is not an explanation—it is a confession of incomplete diagnosis.
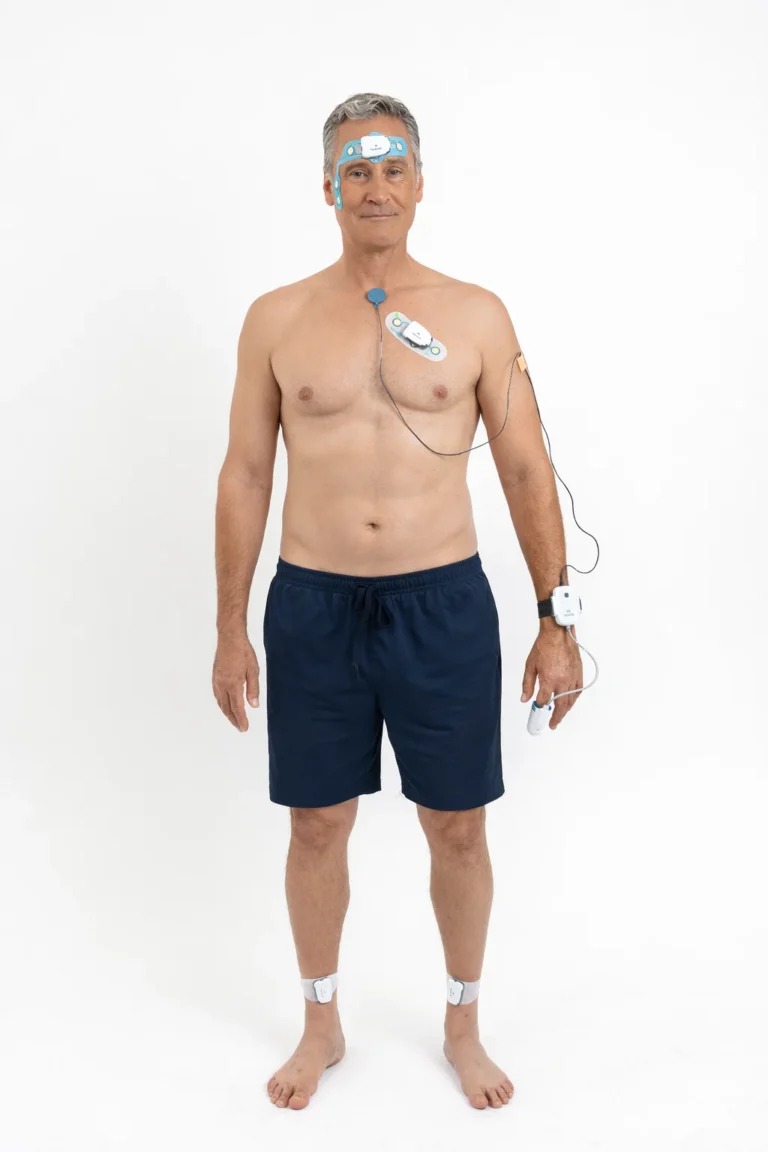
When a patient undergoes a sleep study, is diagnosed with obstructive sleep apnea (OSA), and is successfully managed with CPAP, the expectation is restorative sleep. Yet, many continue to battle fragmented nights and persistent wakefulness. As the industry grapples with the rise of COMISA (Comorbid Insomnia and Sleep Apnea), the medical community must move beyond satisfying the "check-box" of a primary diagnosis and begin investigating the root physiologic disturbances that linger beneath the surface.
The Problem of Search Satisficing
The central hurdle in contemporary sleep medicine is "search satisficing"—the cognitive trap of stopping an investigation the moment a single, plausible diagnosis is found. In 2010, Dr. McCarty introduced the "Five Finger Approach" to combat this, urging clinicians to evaluate five distinct domains: circadian rhythms (thumb), pharmacologic influences (index), medical contributors (middle), psychiatric factors (ring), and primary sleep disorders (pinky).
The emergence of the acronym COMISA has provided a useful label for the overlap of insomnia and OSA, but it has also created a new trap. Relying on Cognitive Behavioral Therapy for Insomnia (CBT-I) as the standard follow-up for these patients is medically sound, but it must not preclude a rigorous search for underlying physiologic triggers. If we stop at the label, we fail the patient.
The Triple Threat: Under-Recognized Causes of Hyperarousal
Dr. McCarty highlights three specific, often overlooked, physiological drivers that contribute to the state of hyperarousal in patients who are otherwise "well-treated."
1. Iron Deficiency: Beyond the Jumpy Legs
While iron deficiency is standard fare in the context of Restless Legs Syndrome (RLS), its role in general insomnia is frequently misunderstood. Iron is essential for dopaminergic signaling and the regulation of inhibitory neurotransmission.
Recent research suggests that brain iron deficiency may induce a "hypoadenosinergic" state. Adenosine is the fundamental molecule that builds "sleep pressure" throughout the day. If iron levels in the central nervous system (CNS) are low, the brain’s response to this pressure may be blunted, leaving the patient in a state of heightened neural activity. Crucially, peripheral blood tests often fail to capture this; a patient may have normal serum hemoglobin but depleted CNS iron stores. Consequently, when clinicians ignore iron status because the patient doesn’t exhibit "textbook" leg movements, they may be missing a vital piece of the sleep-stability puzzle.
2. Iatrogenic Overventilation: When Treatment Backfires
In a paradox that challenges the very foundation of sleep therapy, the equipment designed to save sleep can sometimes ruin it. Positive Airway Pressure (PAP) therapy, while highly effective for airway patency, can induce "Treatment-Emergent Central Sleep Apnea" (TECSA) in susceptible patients.

By aggressively stabilizing the airway, PAP can lead to "iatrogenic hyperventilation." If the device eliminates obstruction too effectively, it can cause the patient’s carbon dioxide levels to drop below the threshold required to trigger a breath. This leads to central events and subsequent arousals. This is particularly prevalent at higher altitudes, such as in the Mountain West, where lower atmospheric oxygen tension already puts patients closer to their apneic threshold. The clinical implication is clear: when a patient uses CPAP faithfully but continues to suffer, the settings themselves—including pressure support, mask type, and even altitude—must be placed in the differential diagnosis.
3. Adaptive Neuroplasticity: The "Borrowed Sleep" Trap
The final, and perhaps most complex, cause of hyperarousal is the legacy of long-term hypnotic medication use. Patients who have relied on benzodiazepines or Z-drugs for years often face a nervous system that has fundamentally rewired itself to accommodate the drug.
This "adaptive neuroplasticity" means that the brain downregulates its natural GABAergic signaling in response to external stimulation. When the patient tries to discontinue the medication, they experience "rebound" or withdrawal-related hyperarousal. This is not merely a recurrence of the original insomnia; it is a new, drug-induced physiologic state. The "borrowed sleep" provided by these medications comes with an interest rate: a nervous system that is now hypersensitive to even minor stimuli. Distinguishing between a return of the original disorder and a withdrawal-induced state is critical for designing a successful, long-term tapering strategy.
Official Guidance and Clinical Implications
The medical community is slowly shifting toward a more nuanced understanding of these phenomena. The 2025 joint clinical practice guidelines on benzodiazepine tapering emphasize that withdrawal is not synonymous with addiction; it is a physiological reality for patients who have used prescribed medications as directed.
Similarly, the American Academy of Sleep Medicine (AASM) has increasingly refined its guidance on iron studies, recognizing that treatment thresholds for RLS and restless sleep disorders differ from those of systemic anemia. These guidelines suggest that the "one-size-fits-all" approach to sleep disorders is rapidly becoming obsolete.
Implications for Future Care
The path forward requires a shift in the clinical mindset:
- Move Beyond the Metric: Device-reported residual AHI (Apnea-Hypopnea Index) is not a proxy for sleep quality. It is a measurement of respiratory metrics, not neural architecture.
- Investigate the Mechanism: When a patient reports persistent wakefulness, the clinician must act as a detective. Is the hyperarousal a byproduct of a low-iron environment? Is the PAP machine over-ventilating the patient? Is the brain struggling to recalibrate after decades of sedation?
- Adopt a Holistic Framework: Using tools like the Five Finger Approach prevents the clinician from settling for a "good enough" diagnosis.
Conclusion: Hyperarousal as a Call to Action
The term "hyperarousal" should be viewed not as a destination, but as a gateway to further inquiry. It is a signal that the homeostatic mechanisms of sleep are being interrupted by something the current diagnostic battery has yet to identify.
As we refine our understanding of COMISA and the underlying drivers of insomnia, the responsibility of the sleep medicine practitioner is to remain perpetually curious. By moving past the jargon and focusing on the underlying physiology, clinicians can provide more than just symptomatic relief; they can provide the structural changes necessary to restore the patient’s natural ability to sleep.
The question is no longer "How do we treat this hyperarousal?" but rather, "What have we missed?" The answers lie in the subtle, complex, and often beautiful interplay of our patients’ biology, their environment, and the very treatments we prescribe.