










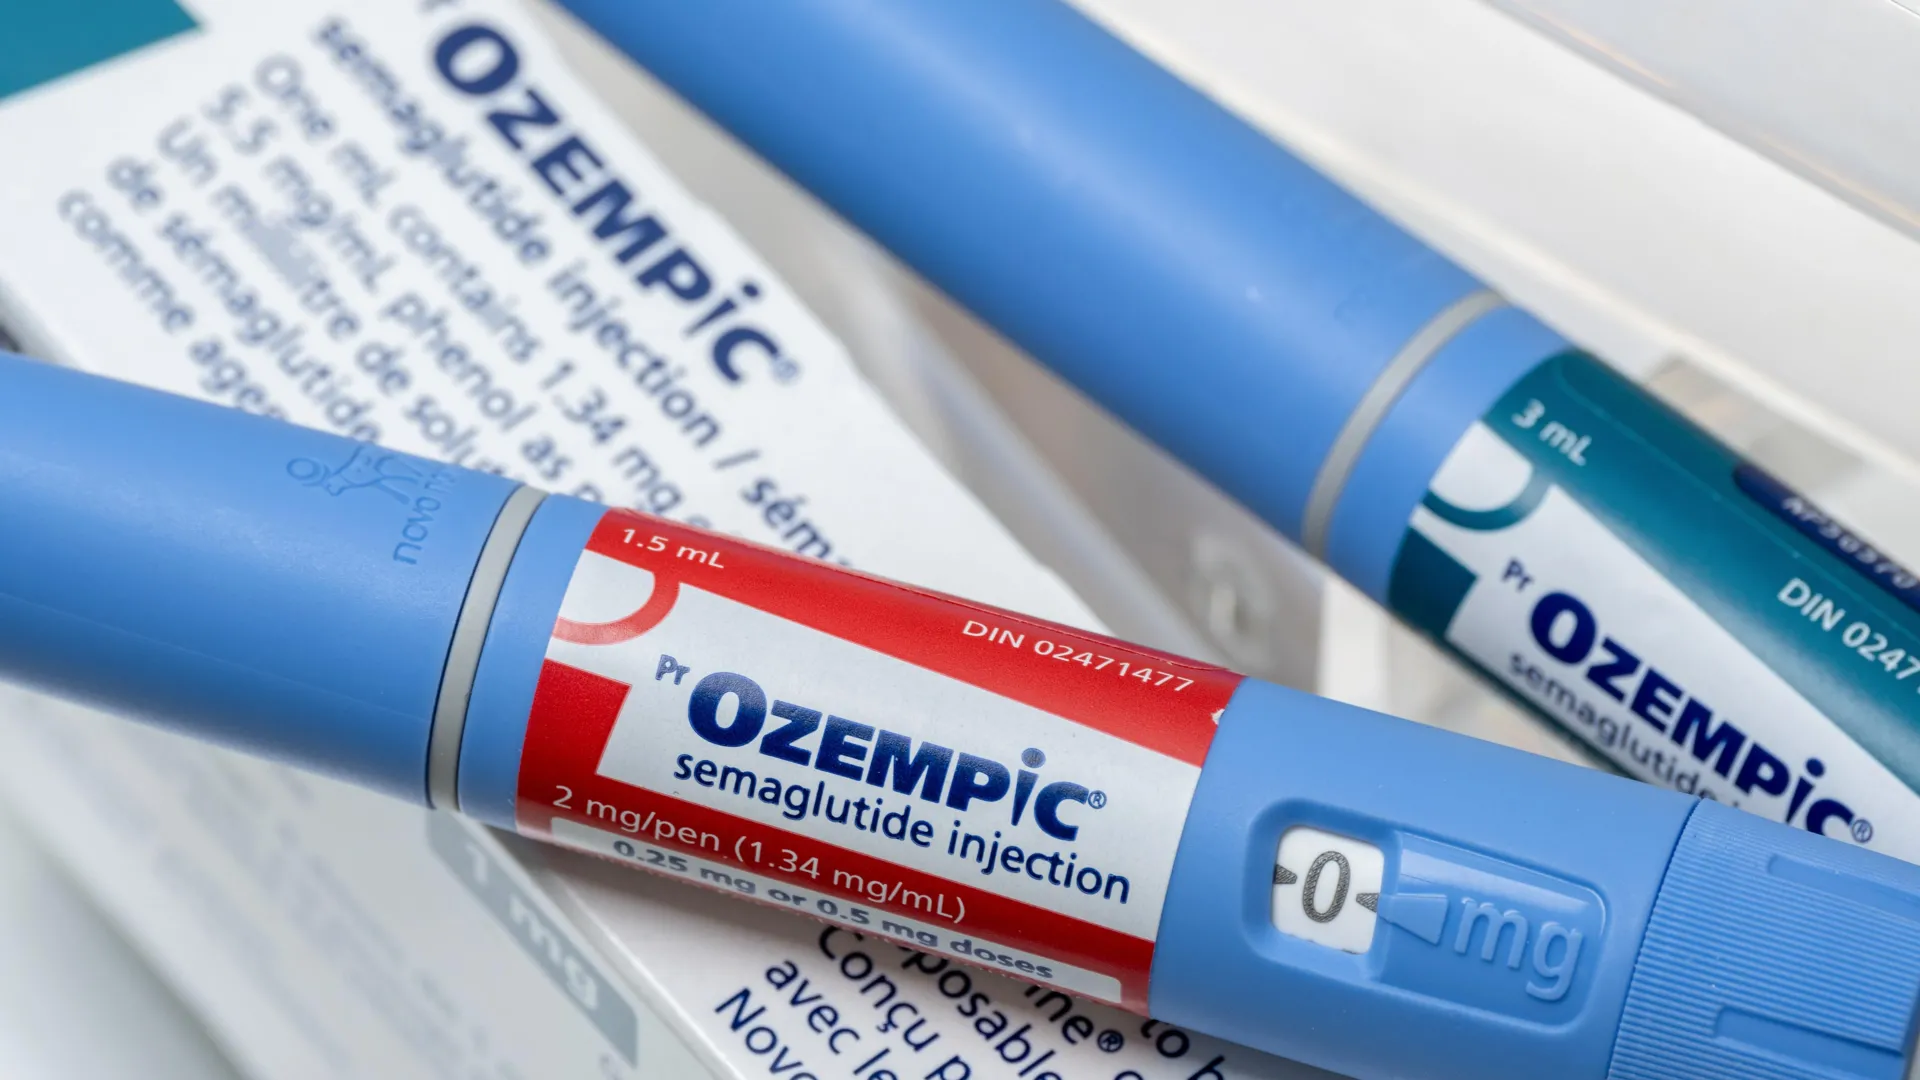
In a significant medical development presented at the European Respiratory Society (ERS) Congress in Barcelona, researchers have unveiled compelling evidence suggesting that semaglutide—a cornerstone medication in the modern treatment of type 2 diabetes and obesity—may offer a potent, unexpected secondary benefit: a drastic reduction in severe asthma attacks.
The study, which utilized extensive real-world electronic health records, indicates that patients with asthma who are prescribed semaglutide experience nearly 40% fewer respiratory exacerbations. While the scientific community is exercising caution, the findings open a new frontier in the understanding of the complex interplay between metabolic health and lung function.
The Core Discovery: A Dual-Action Breakthrough?
The research, led by Professor Chloe Bloom of the National Heart & Lung Institute at Imperial College London, sought to bridge a gap in existing clinical literature. While GLP-1 receptor agonists (the class of drugs to which semaglutide belongs) have been rigorously studied for their impact on glycemic control and weight management, their effect on chronic airway diseases—specifically asthma and Chronic Obstructive Pulmonary Disease (COPD)—has remained largely unexplored in formal clinical trials.
The investigation centered on the hypothesis that the systemic anti-inflammatory properties of GLP-1 agonists might translate into tangible respiratory benefits. By analyzing data from over 20,000 patients across four parallel studies, the researchers discovered that the metabolic improvements induced by these drugs may inadvertently provide a protective layer for the lungs, effectively "quieting" the inflammation that triggers life-altering asthma attacks.
Chronology: From Diabetes Management to Respiratory Research
The journey to this discovery began with the increasing clinical observation that metabolic syndrome and respiratory disease frequently co-exist.
- Initial Observations: As GLP-1 receptor agonists gained widespread popularity for their efficacy in weight loss and diabetes, clinicians noted anecdotal improvements in the overall quality of life for patients with co-morbid respiratory conditions.
- Data Synthesis: Professor Bloom and her colleague, Dr. Bohee Lee, initiated a systematic review of UK electronic health records. They focused on cohorts of patients who had transitioned onto GLP-1 therapies compared to those maintained on sulfonylureas, an older class of diabetes medication.
- The ERS Congress Presentation: In late 2024, the findings were formally presented in Barcelona. The data revealed that the reduction in respiratory flare-ups was not merely a statistical anomaly but a consistent trend across the studied population.
- The Emerging Consensus: Following the presentation, the medical community began to view the findings as a pivot point, shifting the conversation from "metabolic-only" treatments to a more holistic, integrated approach to systemic health.
Supporting Data: Parsing the Numbers
The methodology employed by the research team was robust, involving four distinct parallel studies. Each study tracked between 20,000 and 22,000 patients, ensuring a high level of statistical power. The primary goal was to compare the frequency of acute respiratory attacks—emergency room visits, hospitalizations, and courses of oral corticosteroids—between those on GLP-1s and those on control diabetes medications.
Key Findings:
- The Semaglutide Superiority: While the GLP-1 class generally showed promise, semaglutide emerged as the most potent candidate. Patients with asthma on semaglutide saw a staggering 39–40% reduction in asthma attacks.
- COPD Benefits: Patients suffering from COPD were not left out of the positive outcomes, experiencing a 20% reduction in severe flare-ups.
- The Control Group Gap: Patients receiving traditional sulfonylureas did not demonstrate the same reduction in respiratory events, suggesting that the benefits are specific to the biological mechanism of GLP-1 agonists rather than simply the result of better diabetes management.
These figures are particularly striking because they suggest that the "metabolic-lung axis" is a viable target for pharmacological intervention.
Official Responses and Expert Analysis
The medical establishment has received the news with cautious optimism. While the data is statistically significant, experts are careful to distinguish between an association found in real-world records and a causal relationship that justifies a new clinical prescription guideline.
Dr. Chloe Bloom’s Perspective
Professor Bloom, the study’s lead, has been clear about the boundaries of this research. "The findings from this study are encouraging, but they should not change treatment decisions on their own," she stated during the press conference. She emphasized that while the data suggests a potential clinical benefit, the study is observational. It lacks the rigorous, placebo-controlled randomization of a formal Phase III clinical trial, which is the gold standard for shifting medical practice.
Dr. Alexander Mathioudakis’s Assessment
Dr. Alexander Mathioudakis, Chair of the ERS Group on Airway Pharmacology and Treatment, provided independent context. He noted that the research is one of the most substantial real-world investigations into the link between metabolic therapy and airway health.
"Obesity and metabolic dysfunction are common in airways disease and are often under-recognized as problems that can and should be addressed," Dr. Mathioudakis said. He praised the study for its scope, noting that it highlights the urgent need to integrate respiratory outcomes into future metabolic trials. According to Dr. Mathioudakis, the medical community must move toward "personalized medicine," where the treatment of one condition—such as type 2 diabetes—is chosen specifically because it also helps stabilize a secondary condition like asthma.
The Biological Mechanism: Why Metabolic Health Matters for the Lungs
The scientific community has long understood that obesity is a risk factor for asthma severity. Excess adipose tissue acts as an active endocrine organ, secreting pro-inflammatory cytokines that can infiltrate the airways, increase bronchial hyper-reactivity, and exacerbate the body’s allergic response.
By lowering systemic inflammation, improving insulin sensitivity, and reducing weight, GLP-1 receptor agonists may address the "background noise" of chronic inflammation. When the systemic inflammatory burden is lowered, the airways may become less reactive to common triggers like pollution, allergens, or viral infections. This is a crucial area of future study: determining whether the reduction in asthma attacks is purely a result of weight loss or if semaglutide has direct anti-inflammatory effects on lung tissue.
Implications: The Future of Respiratory Care
The implications of this research are far-reaching. If future clinical trials confirm that semaglutide can act as an adjunct therapy for asthma, it could transform the standard of care for a significant subset of the population.
1. Re-evaluating Treatment Protocols
If a patient presents with both obesity and poorly controlled asthma, clinicians may eventually be guided to prioritize GLP-1 receptor agonists. This shift would represent a move away from "siloed" medicine—where a pulmonologist treats the lungs and an endocrinologist treats the metabolism—toward a holistic management strategy.
2. A Call for New Clinical Trials
The primary takeaway for the scientific community is the necessity for dedicated trials. As Dr. Mathioudakis noted, future research must move beyond glycemic control as the only primary endpoint. Trials must include "respiratory outcomes"—specifically lung function tests, patient-reported quality of life, and the frequency of exacerbations—to truly understand the breadth of these medications’ benefits.
3. Patient Safety and Guidelines
For now, both Dr. Bloom and the broader medical community have issued a stern warning: Patients should not seek out or start GLP-1 receptor agonists specifically to treat their asthma. Current prescribing guidelines remain strict, focusing on type 2 diabetes and obesity management. Misusing these drugs, or using them without medical supervision, carries significant risks, including gastrointestinal side effects and the potential for muscle mass loss if not paired with proper nutrition and exercise.
Conclusion: A New Frontier in Personalized Medicine
The data presented in Barcelona is a compelling reminder that the human body does not operate in distinct, isolated systems. The lungs and the metabolic system are deeply intertwined, and treatments that optimize one may inadvertently provide a vital shield for the other.
As research continues, the medical community will be watching closely to see if the "40% reduction" observed in these real-world records holds up under the rigorous scrutiny of randomized, double-blind trials. If it does, semaglutide may prove to be far more than a weight-loss tool; it could become a cornerstone in the management of chronic airway disease, offering a new lease on life for millions of people struggling to breathe easy.
For now, the message to patients and practitioners alike is one of patience and continued scientific inquiry. The "metabolic-lung axis" is open for exploration, and the answers found therein may redefine the landscape of respiratory health in the coming decade.







