









For millions of Americans, the diagnosis of Obstructive Sleep Apnea (OSA) is a life-altering event. Characterized by repetitive airway collapses during sleep, this condition leads to fragmented rest, daytime fatigue, and significant long-term cardiovascular risks. As medical science evolves, the conversation around treatment has expanded beyond the standard Continuous Positive Airway Pressure (CPAP) machine to include pharmaceutical interventions, specifically Glucagon-like peptide-1 (GLP-1) receptor agonists.
While medications like Ozempic have captured headlines for their efficacy in weight management, their role in treating sleep apnea is nuanced, involving complex insurance landscapes, FDA regulations, and the fundamental physiology of weight-related breathing disorders.
The Physiological Link: Why Weight Matters in Sleep Apnea
Obstructive sleep apnea is primarily mechanical. It occurs when the muscles in the throat relax excessively, allowing the airway to narrow or close during sleep. These pauses in breathing, known as apneas or hypopneas, can occur dozens of times per hour, forcing the body to briefly awaken to resume respiration.
Excess body weight—particularly adipose tissue concentrated around the neck and throat—is the single most significant risk factor for OSA. Data indicates that approximately 31% of individuals with OSA live with obesity, while 44% are classified as overweight. This excess tissue acts as a physical obstruction, crowding the airway and making collapse more likely once the muscles lose their tone during the sleep cycle.
The connection between weight loss and symptom relief is robust. Clinical studies have demonstrated a clear dose-response relationship: a 20% reduction in Body Mass Index (BMI) is associated with a 57% reduction in the severity of sleep apnea symptoms. By reducing the neck circumference and fat deposits surrounding the pharyngeal airway, patients often see a dramatic improvement in their Apnea-Hypopnea Index (AHI) scores.
Chronology of GLP-1 Development and OSA Approval
The journey of GLP-1 medications from diabetes management to weight loss and sleep apnea treatment has been rapid:
- Initial Approval: GLP-1s were originally engineered to treat Type 2 diabetes by mimicking hormones that regulate insulin secretion and appetite. Ozempic (semaglutide) became the gold standard in this class.
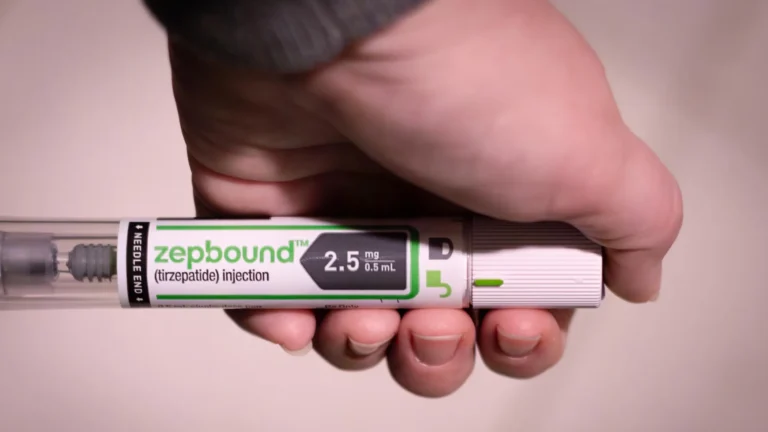
- The Weight Loss Shift: As patients reported significant weight loss as a "side effect," the pharmaceutical industry pivoted. Wegovy (a higher-dose formulation of semaglutide) and Zepbound (tirzepatide) were introduced specifically for weight management.
- The 2024 Milestone: A landmark moment occurred in 2024 when the U.S. Food and Drug Administration (FDA) officially approved Zepbound (tirzepatide) for the treatment of moderate to severe OSA in adults with obesity. This decision was based on clinical trials showing that patients achieved significant reductions in their AHI, proving that the drug directly addresses the root cause of the obstruction for a specific patient population.
The Current Insurance Landscape: Why Coverage Isn’t Guaranteed
Despite the clinical efficacy, the path to obtaining these medications through insurance is rarely straightforward.
The "Off-Label" Hurdle
Ozempic, while highly effective for weight loss, is FDA-approved solely for Type 2 diabetes. Consequently, most insurance providers refuse to cover it for OSA. When physicians prescribe it for weight-related sleep apnea, it is considered "off-label." Most insurers maintain strict policies against covering medications for off-label use, regardless of the patient’s medical need.
The Rise of Zepbound
Because Zepbound has received official FDA approval for sleep apnea, the tide is beginning to turn. Many health plans are adding it to their formularies. However, this comes with "prior authorization" requirements. To secure coverage, patients are often required to prove:
- BMI Thresholds: A documented BMI that meets the insurer’s criteria for obesity.
- CPAP Failure: Documentation that the patient has attempted CPAP therapy and either failed to tolerate it or found it ineffective.
- Structured Weight Loss: Evidence that the patient has engaged in a supervised diet and exercise program without achieving the desired clinical outcomes.
Medicare and Medicaid
Medicare coverage for GLP-1s remains a contentious issue. While Medicare generally does not cover weight-loss drugs, the approval of Zepbound for a medical diagnosis like OSA provides a pathway for coverage. Currently, some Medicare Advantage plans may offer coverage, often requiring a copay of approximately $50 per month, though this varies significantly by region and plan tier.
How to Check Your Coverage and Advocate for Yourself
If you and your healthcare provider believe a GLP-1 medication is a necessary component of your sleep apnea treatment, take the following steps to navigate the administrative burden:
1. Consult the Formulary
Your insurer’s website is the first point of contact. Search for the "Formulary" or "Drug List." This document categorizes medications into "tiers," which dictate your out-of-pocket costs and whether prior authorization is required.
2. Leverage the Appeals Process
A denial is not necessarily the end of the road. If your initial request is rejected, you have the right to an appeal. This is where your doctor’s documentation becomes critical. A "Letter of Medical Necessity" from your sleep specialist, detailing your AHI, your failed attempts at other therapies (like CPAP), and your weight-related comorbidities (like hypertension), can significantly strengthen your case. Most plans allow for an internal appeal within six months of a denial, followed by an external, third-party review if necessary.
3. Contact Member Services
If digital portals are unclear, call the customer service number on the back of your insurance card. Specifically ask, "What are the clinical criteria for prior authorization for GLP-1 medications in the context of obstructive sleep apnea?"
Lifestyle Alternatives and Complementary Treatments
It is vital to recognize that medications are not a panacea. Lifestyle modifications remain the bedrock of OSA treatment. Even if you secure a prescription, the following remain essential:
- Caloric Deficit: Weight loss is achieved through a consistent calorie deficit. Working with a registered dietitian can help create a plan that is sustainable rather than restrictive.
- Physical Activity: The Department of Health and Human Services recommends 150 to 300 minutes of moderate-intensity exercise per week. Resistance training is particularly beneficial for sleep apnea patients, as increased muscle mass improves metabolic rate, making it easier to maintain weight loss long-term.
- Dietary Adjustments: Reducing intake of ultra-processed foods, alcohol, and sugary beverages can reduce systemic inflammation and water retention, both of which can exacerbate airway swelling.
Implications for the Future of Sleep Medicine
The integration of GLP-1s into the sleep apnea toolkit signals a shift toward a more holistic approach to chronic disease management. We are moving away from treating sleep apnea as an isolated airway problem and toward treating it as a metabolic and systemic issue.
However, the high cost of these medications—often ranging from $500 to over $1,000 per month out-of-pocket—creates a disparity in access. As more data emerges from long-term studies, it is expected that insurance guidelines will continue to evolve, hopefully creating more equitable access for those whose health depends on addressing the root causes of their sleep apnea.
Medical Disclaimer
The information provided in this article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition or medication. Never disregard professional medical advice or delay in seeking it because of something you have read here.
Frequently Asked Questions (FAQ)
Q: Does Medicare cover Ozempic for sleep apnea?
A: No. Medicare does not cover Ozempic for sleep apnea or weight loss. However, it may provide coverage for Zepbound under specific circumstances, as Zepbound is FDA-approved for OSA. Patients typically face a monthly copay of approximately $50 under these plans.
Q: What is the average cost of GLP-1s without insurance?
A: Costs vary, but medications like Ozempic can exceed $499 per month out-of-pocket. Always check the manufacturer’s website for potential savings programs or discount cards, which may lower the cost for eligible patients.
Q: How long can I expect insurance to cover these medications?
A: Coverage is typically granted in six-to-12-month increments. Continued coverage almost always requires proof of progress, such as documented weight loss or improved AHI scores, verified by your physician.
Q: Can I use GLP-1s instead of a CPAP machine?
A: You should never stop using your CPAP machine without consulting your doctor. GLP-1s are intended to be a complementary therapy. Your doctor will determine if your improvements are significant enough to reduce or eliminate the need for PAP therapy based on follow-up sleep studies.