








For the first time since 2018, the medical landscape regarding cardiovascular health has undergone a significant transformation. On March 28, at the American College of Cardiology’s (ACC) 75th Annual Scientific Session in New Orleans, the ACC and the American Heart Association (AHA) jointly unveiled updated clinical guidance for the screening and management of blood cholesterol. Published simultaneously in the Journal of the American College of Cardiology and Circulation, these new recommendations represent a pivot from reactive, mid-life intervention to a strategy defined by lifelong, personalized risk mitigation.
The release of these guidelines coincides with a broader academic push for preventative clarity, underscored by the recent publication of "The ABCs of Cardiovascular Disease Prevention: Communicating What We Know in 2026" in the American Journal of Preventive Cardiology. Together, these documents signal that the medical community is moving toward a more nuanced, data-driven approach to staving off the world’s leading cause of death: cardiovascular disease.
Main Facts: The New Standard for Lipid Management
The 2026 guidance is anchored in a fundamental biological premise: lower LDL cholesterol (the "bad" cholesterol) is categorically better for the longevity of the vascular system. However, the update moves beyond simple numbers. It mandates a comprehensive look at an individual’s lipid profile, including lipoprotein(a) or Lp(a), and demands that clinicians consider non-traditional risk factors—such as pregnancy complications and chronic inflammatory conditions—when calculating a patient’s long-term risk.
Core Pillars of the Updated Guidance:
- Aggressive LDL Targets: For those without existing cardiovascular disease, the optimal threshold remains below 100 mg/dL. However, for those at intermediate risk, the target drops to below 70 mg/dL, and for high-risk individuals, the goal is now less than 55 mg/dL.
- Earlier Screening: The guidelines push for the initiation of screening at younger ages, particularly for those with a family history of atherosclerosis or genetic conditions like familial hypercholesterolemia, where screening is now recommended as early as age 9.
- The PREVENT Calculator: Replacing older models that focused only on 10-year risk for those over 40, the new "Predicting Risk of Cardiovascular Disease EVENTs" (PREVENT) tool allows for 10- and 30-year risk assessment starting at age 30, incorporating kidney function and blood sugar data for higher accuracy.
- Diversified Pharmacotherapy: While statins remain the cornerstone of treatment, the guidelines provide explicit protocols for the use of ezetimibe, bempedoic acid, and PCSK9 inhibitors, ensuring that patients who are statin-intolerant or require more aggressive lowering have clear paths to treatment.
Chronology of a Paradigm Shift
The journey toward these 2026 guidelines has been marked by a decade of rapidly evolving clinical trials and large-scale data collection.
- 2018: The previous ACC/AHA cholesterol guidelines were released, which served as the gold standard for several years, emphasizing statin intensity based on 10-year risk.
- 2019–2024: A period of intensive research, including the VESALIUS-CV trial and various studies on PCSK9 inhibitors, revealed that "lower is better" could be applied more aggressively than previously thought, even in primary prevention settings.
- March 2026: The official unveiling at the ACC’s 75th Annual Scientific Session in New Orleans marked the culmination of years of collaborative synthesis between the ACC, the AHA, and various cardiovascular health organizations.
- Post-March 2026: The implementation phase begins, with health systems across the United States updating their Electronic Health Records (EHR) to integrate the PREVENT calculator and revised lipid screening protocols.
Supporting Data: Why the Change?
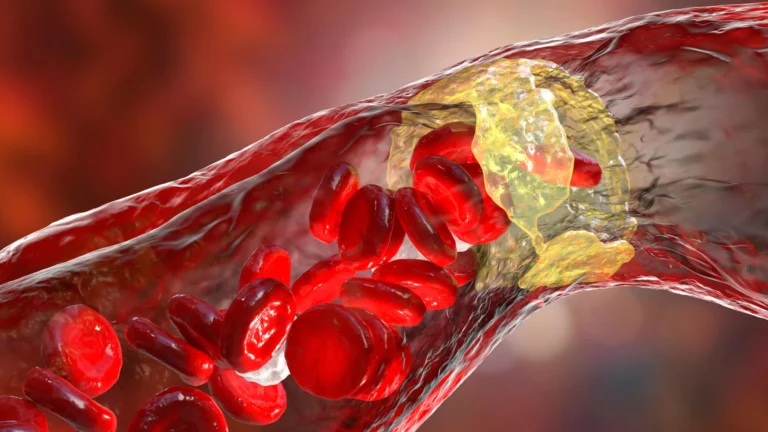
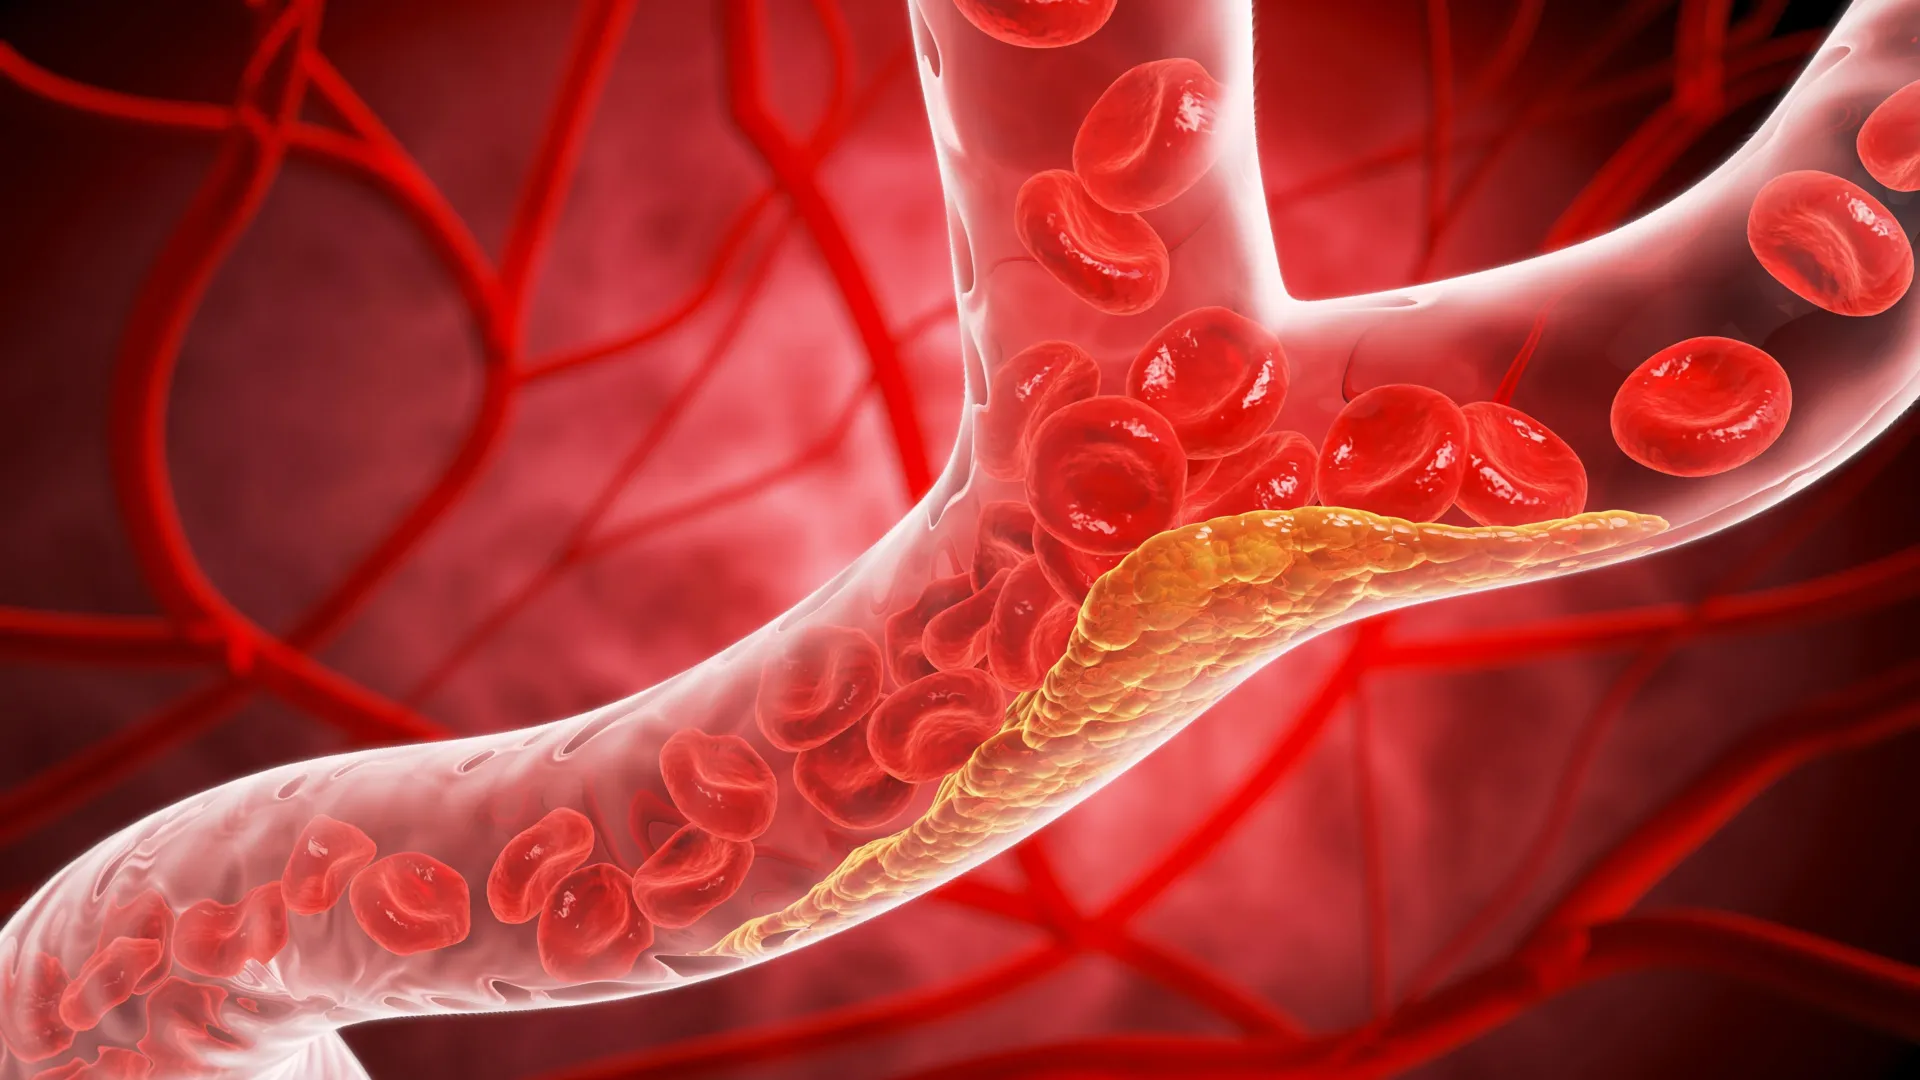
The urgency behind these updates is driven by sobering statistics. Approximately one in four American adults currently lives with elevated LDL-C levels, a primary driver of atherosclerosis. When lipids accumulate in the arterial walls, they form plaques that not only restrict blood flow but can rupture, leading to acute myocardial infarction (heart attack) or ischemic stroke.
The Power of Big Data
The transition to the PREVENT calculator is perhaps the most significant analytical leap in the new guidelines. While the previous risk assessment model relied on a dataset of approximately 26,000 individuals, the PREVENT tool is built upon the health records of 6.6 million people. By including markers such as kidney function and blood sugar—indicators often ignored in simple cholesterol calculations—the new tool provides a 30-year trajectory of risk that is far more representative of the modern, diverse American population.
The Role of Genetics and Inflammation
The inclusion of Lp(a) testing is a direct response to data indicating its role as an independent, inherited risk factor. Clinical evidence shows that levels of 125 nanomoles per liter (nmol/L) raise heart disease risk by 40%, while levels of 250 nmol/L double that risk. By mandating a one-time test for this lipid, the guidelines ensure that patients with "hidden" genetic risks are identified long before they manifest clinical symptoms.
Official Responses: Insights from the Writing Committee
The experts behind the guidelines emphasize that while medication is a vital tool, the "lifestyle-first" approach remains the bedrock of cardiovascular medicine.
Dr. Roger S. Blumenthal, director of the Johns Hopkins Ciccarone Center for the Prevention of Cardiovascular Disease and chair of the guideline writing committee, was clear about the intent of these changes. "We know that bringing elevated lipids and blood pressure down in young adults supports optimal heart and vascular health throughout a person’s life," Blumenthal noted during the New Orleans session. He reiterated that 80% to 90% of cardiovascular disease is linked to modifiable factors, reinforcing that smoking cessation, physical activity, sleep hygiene, and diet remain the most critical prescriptions a doctor can write.
Dr. Seth Martin, a cardiologist and fellow committee member, emphasized the proactive nature of the new strategy. "Shifting the paradigm toward proactive prevention strategies earlier in life can meaningfully change the trajectory of cardiovascular disease and lead to better health outcomes for people decades later," Martin stated. The committee’s goal is to move the medical field away from "treating the event" and toward "preserving the vessel."
Implications: A New Era for Patients and Clinicians
The adoption of the 2026 guidelines will have far-reaching implications for clinical practice and patient advocacy.
For the Clinician
Doctors are now empowered—and expected—to look at a wider array of "risk enhancers." For patients who fall into the "borderline" or "moderate" risk categories, clinicians are encouraged to use high-sensitivity C-reactive protein (hsCRP) tests to measure inflammation and coronary artery calcium scans to visualize actual plaque buildup. This precision medicine approach allows for "shared decision-making," where the patient and doctor can weigh the potential benefits of aggressive therapy against the necessity of lifestyle interventions.
For the Patient
The most profound implication for patients is the normalization of early screening. By identifying risk factors as early as age 30, or even at age 9 for those with familial predispositions, the medical system is effectively promising a longer "healthspan." Patients will no longer be told to "wait and see" if their cholesterol numbers improve; instead, they will be given actionable, long-term plans that account for their specific genetic, social, and physiological history.
Future Horizons
The guidelines are not a static end point. An accompanying editorial suggests that as more data emerges from trials like VESALIUS-CV, future iterations may push for even more aggressive targets, potentially aiming for LDL-C levels below 55 mg/dL for an even broader swath of the population with moderate atherosclerosis.
The 2026 Guideline on the Management of Dyslipidemia is a testament to the fact that while heart disease remains the primary threat to the American public, our ability to predict, identify, and intercept that threat has never been more sophisticated. By prioritizing early intervention, incorporating advanced predictive data, and embracing a personalized treatment philosophy, the ACC and AHA have laid a foundation for a future where cardiovascular events are the exception, not the rule.