







For decades, cardiovascular medicine has focused heavily on the traditional "Big Three" of heart health: cholesterol, blood pressure, and smoking. However, a landmark study involving nearly half a million adults has unveiled a more insidious culprit, one that operates in the shadows of our daily lives: chronic, low-level inflammation.
Led by researchers at the MRC Laboratory of Medical Sciences (LMS) and Imperial College London, this extensive analysis suggests that the stresses of modern existence—ranging from socioeconomic hardship to psychological distress—are not merely abstract burdens. Instead, they appear to leave a tangible, structural "scar" on the heart, potentially shortening lifespans and significantly elevating the risk of heart attacks and strokes long before the first symptom appears.
The Mechanism: When the Immune System Never Sleeps
To understand the findings, one must first understand the biological paradox of inflammation. In its acute form, inflammation is a hero; it is the body’s essential response to injury or infection, rushing white blood cells to a site of damage to begin the healing process. However, the study highlights the "darker side" of this process: chronic, systemic inflammation.
Chronic inflammation occurs when the immune system’s "on" switch gets stuck. Rather than retreating once an immediate threat has passed, the immune system remains mildly, persistently activated. This state of perpetual biological vigilance has previously been implicated in diabetes and cancer. Now, it is firmly linked to the physical remodeling of the heart.
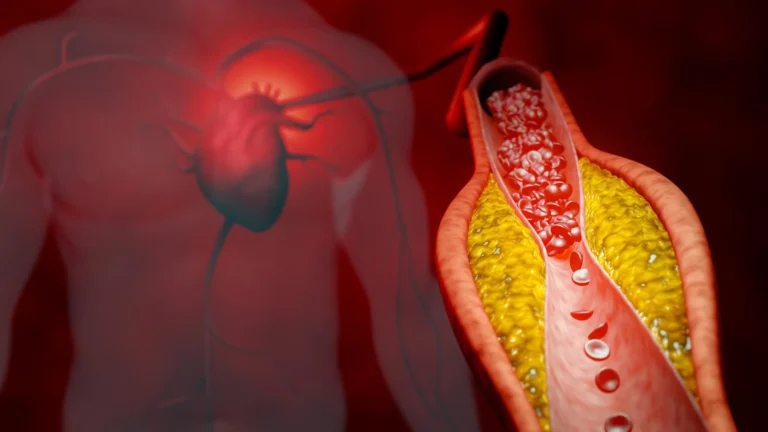
According to the research, this persistent immune activity leads to a cascade of negative structural changes. Over years of silent accumulation, the heart walls may thicken, the chambers may shrink, and the heart’s ability to fill with blood efficiently—known as cardiac filling—begins to deteriorate. These changes are not the result of a single catastrophic event, but a slow, quiet erosion of cardiac health that often goes undetected until it culminates in heart failure or a major cardiovascular event.
Chronology of Discovery: A Massive Data Undertaking
The scale of this research marks a watershed moment in cardiovascular epidemiology. By leveraging the UK Biobank, the researchers analyzed data from approximately 480,000 individuals. The methodology was as rigorous as it was expansive, integrating three distinct data streams:
- Biochemical Markers: The team utilized a blood marker known as GlycA (glycoprotein acetyls) to measure systemic inflammation levels. GlycA serves as a robust indicator of the body’s overall inflammatory state.
- Advanced Imaging: Using large-scale cardiac imaging, the researchers were able to visualize the physical structure of the heart, allowing them to correlate inflammatory markers with real-world changes in muscle thickness and chamber volume.
- Genomic Mapping: By incorporating genetic information, the study provided a rare glimpse into how an individual’s inherent biological makeup influences their susceptibility to environmental and lifestyle-driven inflammation.
By tracking these variables over time, the team was able to build a longitudinal picture of how lifestyle pressures translate into physiological pathology.
Supporting Data: The 43% Threshold
The statistical findings of the study are stark. When researchers compared the cohort with the highest 20% of inflammation levels to the cohort with the lowest 20%, the discrepancy in health outcomes was profound.
The group with the highest levels of GlycA faced a 43% higher risk of suffering a heart attack or stroke. Crucially, this elevated risk held true even for participants who had no history of pre-existing heart disease. This suggests that inflammation acts as an independent, potent precursor to cardiovascular catastrophe.
Furthermore, the data revealed a compelling intersection between social determinants and biological health. The study confirmed that higher inflammation was strongly correlated with socioeconomic disadvantage, chronic psychological distress, and established risk factors like obesity and tobacco use. The "silent remodeling" of the heart—the thickening of walls and the reduction of chamber efficiency—was found to be the biological bridge connecting these external pressures to internal disease.
Official Perspectives: Translating Science into Strategy
The significance of these findings has drawn attention from some of the leading voices in cardiovascular science. Professor Declan O’Regan, Chair of Cardiovascular AI at Imperial College London and Head of the Computational Cardiac Imaging Group at the LMS, believes the implications are transformative.
"Our study suggests that millions of people could be living with hidden inflammation, which is slowly changing their heart and causing long-term damage," Professor O’Regan stated. "Chronic inflammation is complicated, but we know it’s tied to our health and driven by a range of lifestyle and economic factors—meaning people may be at more risk just because of their surroundings, their economic status, and their family’s health."
Professor Bryan Williams, Chief Scientific and Medical Officer at the British Heart Foundation, echoed these sentiments, emphasizing the need for a shift in how we approach heart disease prevention.
"This large-scale study found people with higher levels of inflammation experienced silent changes to the structure of their hearts," Williams noted. "The research provides valuable insights into how our genes and lifestyle factors… can converge to trigger inflammation. It is to be hoped that anti-inflammatory medicines could become an important tool in preventing cardiovascular disease."
Implications: A New Era of Preventative Medicine
The study’s most optimistic takeaway lies in the potential for intervention. The researchers identified specific inflammatory proteins, notably within the interleukin-1 and TNF families, that appear to drive this structural heart damage.
1. Targeted Pharmacotherapy
Because several of these inflammatory proteins are already targets for existing drugs currently in clinical trials, the medical community is moving closer to a future where we can "switch off" chronic inflammation before it results in heart failure. Anti-inflammatory therapies, if successfully adapted for cardiovascular use, could provide a secondary line of defense alongside traditional treatments like statins and antihypertensives.
2. Biomarker-Driven Screening
The study suggests that incorporating GlycA blood tests into routine physical examinations could act as an early-warning system. By combining these inflammatory blood markers with genetic risk scores, clinicians may be able to identify "at-risk" patients years before they present with hypertension or chest pain, allowing for lifestyle interventions that could potentially reverse or halt the damage.
3. Addressing the Social Determinants of Health
Perhaps the most challenging implication is the recognition that heart health is inextricably linked to socioeconomic status. The study underscores that poverty and psychological distress are not just "life stressors"—they are physiological stressors that trigger immune responses. This reinforces the argument that public health policy, urban planning, and economic support systems are, in effect, public health interventions. Improving living conditions and reducing inequality are now as much about heart health as they are about social justice.
Conclusion: Resilience in the Face of Risk
While the findings present a sobering picture of how environmental and social pressures can literally shape the heart, the researchers are quick to offer a message of hope. Genetic predisposition or difficult life circumstances do not render heart disease inevitable.
The human heart is remarkably resilient, and the body’s inflammatory response is, at its core, a malleable system. By tackling the root causes of inflammation—reducing tobacco use, managing body weight, and addressing the psychosocial impacts of our environments—individuals can significantly mitigate their risk.
As the medical community digests this data, the focus is shifting toward a more holistic model of cardiovascular care. The future of heart health may lie not just in the operating room or the pharmacy, but in a deeper understanding of how our lives—our work, our stress, and our communities—shape the very organ that keeps us alive. The "hidden" damage is no longer hidden; it is now a documented target for the next generation of preventative medicine.