





For decades, the standard barometer for heart health in the United States has been the "bad" cholesterol test—the LDL (low-density lipoprotein) panel. Millions of Americans undergo this ritual annually, fasting before a blood draw to determine their risk of cardiovascular events. However, a groundbreaking study from Northwestern Medicine suggests that this conventional approach may be missing the forest for the trees. According to new research published in the journal JAMA, a different metric—apolipoprotein B (apoB)—offers a significantly more precise way to identify patients who require aggressive intervention to prevent heart attacks and strokes.
This shift in perspective arrives at a critical juncture in American healthcare, where heart disease remains the leading cause of mortality and a primary driver of ballooning medical expenditures. As clinical guidelines evolve to encourage earlier and more proactive cholesterol-lowering therapies, the need for diagnostic accuracy has never been more pressing.
The Main Facts: A New Gold Standard for Risk Assessment
The core finding of the Northwestern study is that apoB, a protein that acts as a structural scaffold for cholesterol-carrying particles, provides a more granular and accurate assessment of cardiovascular risk than traditional LDL or non-HDL cholesterol tests.
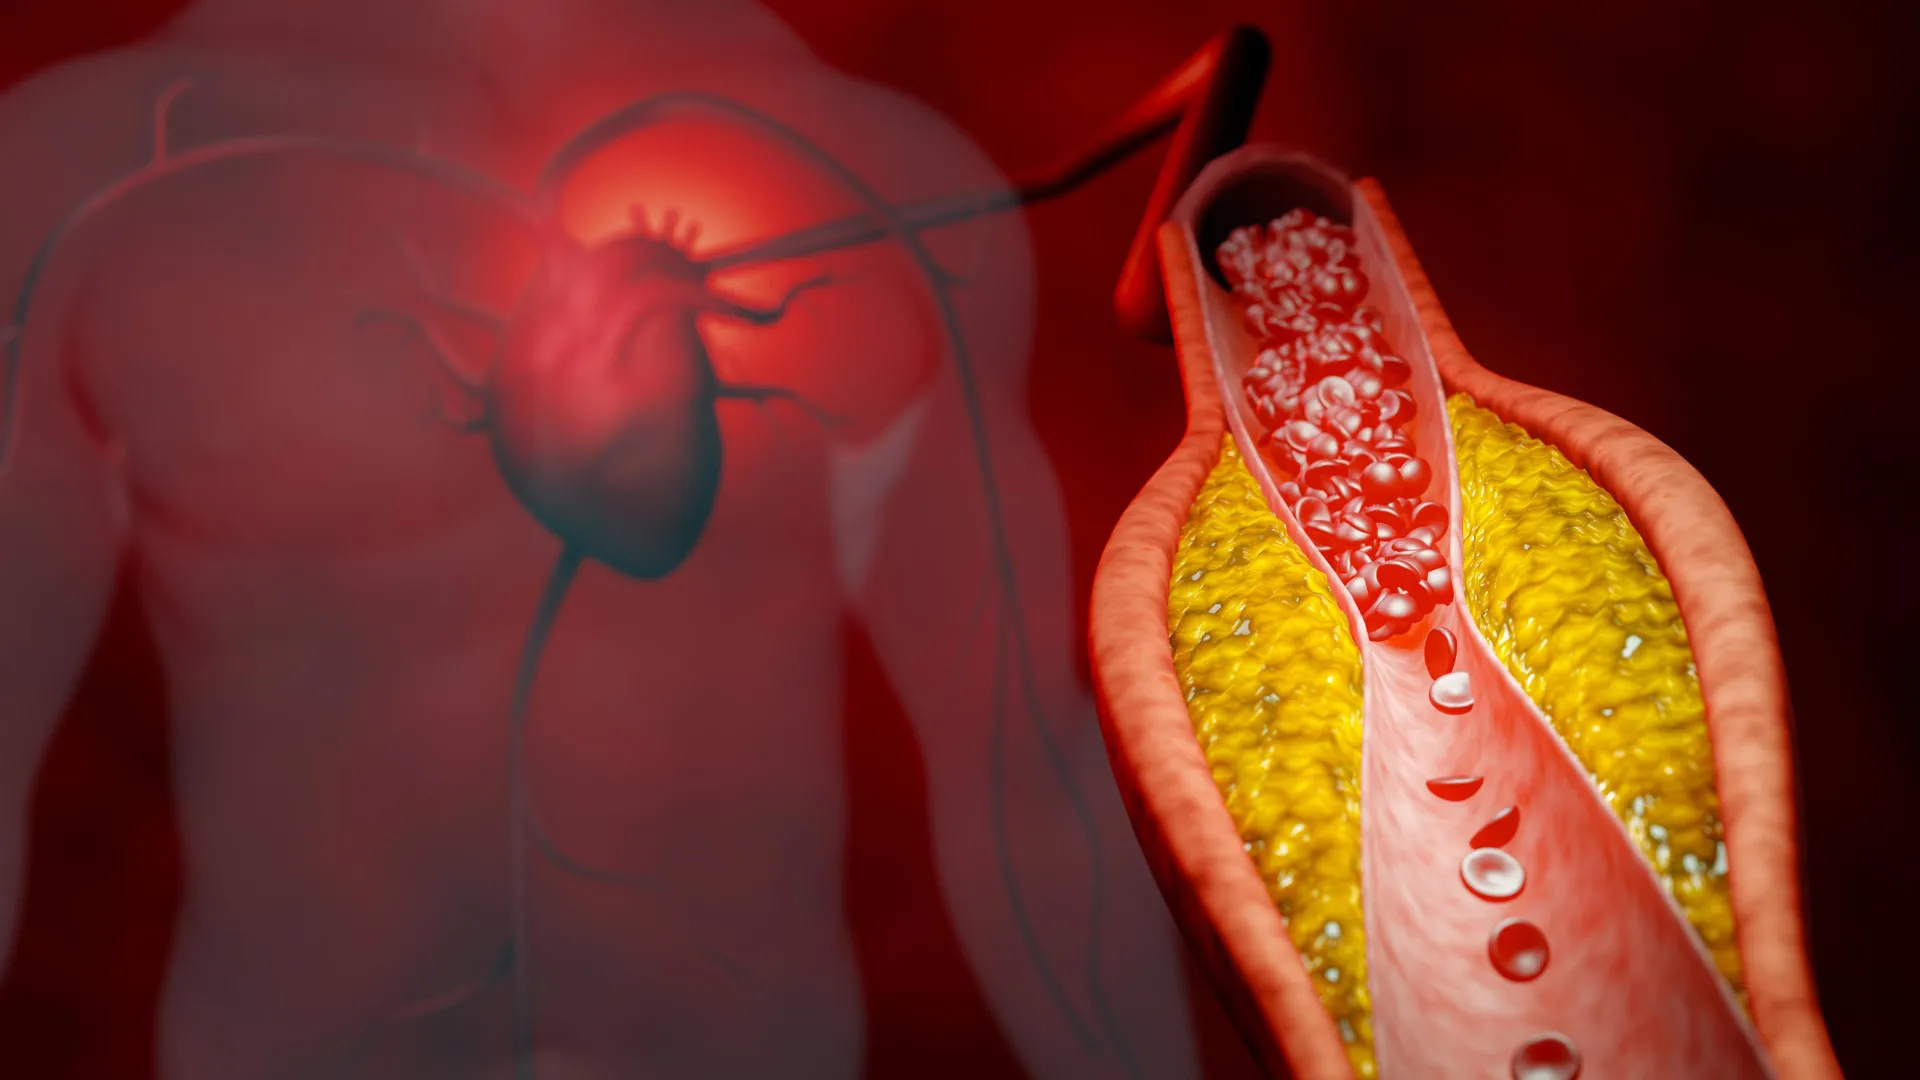
While standard tests measure the amount of cholesterol, apoB measures the total number of harmful, atherogenic particles circulating in the bloodstream. Because it is these particles that ultimately infiltrate artery walls and form the plaques responsible for restricting blood flow, experts argue that apoB is a more direct indicator of danger.
The study, led by Dr. Ciaran Kohli-Lynch, assistant professor of preventive medicine at Northwestern University Feinberg School of Medicine, indicates that utilizing apoB as the primary guide for escalating cholesterol-lowering therapy—such as statins and ezetimibe—would prevent a greater number of heart attacks and strokes compared to the current standard of care. Critically, the researchers concluded that this approach is not only clinically superior but also highly cost-effective, providing significant value for the U.S. healthcare system.
Chronology: The Evolution of Cholesterol Management
To understand the magnitude of this shift, one must look at the history of cardiovascular risk management.
The Era of LDL Dominance
Since the introduction of the lipid panel, the medical community has focused on LDL-C as the primary target for therapy. Physicians have long relied on thresholds for LDL to determine when to initiate statin treatment. While this approach has undeniably saved countless lives, it has also faced scrutiny for its limitations. LDL-C testing provides a measurement of the mass of cholesterol within particles, but it does not account for the concentration of the particles themselves.
The Rise of Non-HDL
In recent years, guidelines began to emphasize non-HDL cholesterol (total cholesterol minus HDL), which accounts for all "bad" cholesterol particles. While this was an improvement over LDL-C alone, it still functioned as a surrogate measurement rather than a direct count of the particles prone to causing plaque.
The Current Turning Point
The publication of the Northwestern study marks a formal transition in the scientific debate. By utilizing advanced computer modeling to simulate the lifespans of 250,000 U.S. adults eligible for statin therapy, researchers have provided the first comprehensive, multi-decade analysis of how shifting to an apoB-centered strategy would impact public health outcomes. The study’s results—which favor apoB—provide a foundation for a paradigm shift in how cardiologists and primary care physicians approach preventative medicine.
Supporting Data: The Power of Simulation
To validate the clinical and economic impact of apoB, the research team at Northwestern developed a sophisticated computer simulation. The model focused on adults who were candidates for statin therapy but had not yet developed cardiovascular disease (primary prevention).
Three Strategies Compared
The simulation tested three distinct protocols for managing cholesterol:
- The LDL-C Approach: Using LDL-C levels as the target for medication adjustment.
- The Non-HDL-C Approach: Using non-HDL-C levels as the target.
- The ApoB Approach: Using apoB particle counts as the primary target.
In each scenario, if a patient failed to meet their specific target, the simulation automatically escalated treatment—first by optimizing statin dosage and then by introducing ezetimibe, a medication that prevents cholesterol absorption in the small intestine.
Findings on Outcomes and Value
The data revealed that the apoB-led strategy consistently outperformed the alternatives. By focusing on the particle count, physicians were able to identify "residual risk" that LDL-C and non-HDL-C tests often failed to detect.
- Health Outcomes: The apoB strategy led to a measurable reduction in the incidence of myocardial infarction (heart attack) and stroke.
- Cost-Effectiveness: Despite the potential for slightly higher upfront diagnostic costs associated with an additional blood test, the long-term savings—derived from preventing expensive hospitalizations, cardiac procedures, and chronic care—resulted in a favorable economic profile.
Official Responses and Expert Perspective
The implications of these findings have been met with interest from the broader medical community. Dr. Ciaran Kohli-Lynch, the study’s lead author, emphasizes that while the test is currently underutilized, the barriers to implementation are not insurmountable.
"We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice," says Dr. Kohli-Lynch. "This is the first comprehensive analysis to show that using apoB to guide cholesterol treatment is also cost-effective."
The study’s co-authors, including Dr. John Wilkins and Dr. Samuel Luebbe, stress that the logistical challenge of adding an extra blood test is a small price to pay for the increased precision it offers. Historically, the primary argument against routine apoB testing has been the extra cost and patient inconvenience. However, the study directly addresses this by demonstrating that the "extra money" spent on testing is offset by the downstream benefits of a healthier population.
Implications: A New Roadmap for Preventive Cardiology
The release of these findings coincides with updated guidelines from the American Heart Association and ten other medical organizations, which suggest that more Americans—particularly younger adults—should begin cholesterol-lowering therapy earlier in life.
The Need for Precision
As the pool of patients on statins grows, the need to distinguish between those who are effectively managed and those who remain at high risk becomes paramount. If a patient is taking a statin but still possesses a high count of apoB particles, their risk of a cardiovascular event remains elevated. Current practices might miss this discrepancy, whereas an apoB-guided strategy would flag it immediately, allowing for the timely addition of non-statin medications.
Overcoming Barriers to Adoption
Despite the clinical evidence, the medical system is often slow to adopt new diagnostic standards. Widespread integration of apoB testing will require:
- Clinical Education: Physicians must be trained to interpret apoB levels and adjust treatment accordingly.
- Laboratory Standardization: Routine inclusion of apoB in lipid panels needs to become as standard as LDL-C.
- Insurance Coverage: To ensure accessibility, health insurance providers must recognize the long-term cost-benefit of this testing, as highlighted by the Northwestern research.
A Future of Personalized Care
The transition to apoB testing represents a shift toward "precision cardiology." Instead of a one-size-fits-all approach to cholesterol, clinicians are moving toward a model where treatment is tailored to the actual biological risk factors of the individual patient. By measuring the particles that actually cause plaque, medicine can move from reacting to heart attacks to preventing them before they happen.
As heart disease continues to drain resources and claim lives, the evidence provided by this study suggests that the path forward is clear. By embracing more accurate diagnostic tools like apoB, the healthcare system has the opportunity to make a quantum leap in the prevention of the world’s leading killer, ensuring a future where cardiovascular risk is managed with data-driven precision rather than broad-stroke assumptions.
This study is not merely a report on a new test; it is a call to modernize the standards of preventative care to match the complexity of human biology. As research continues to solidify the link between apoB and cardiovascular outcomes, it is increasingly likely that this test will become the new cornerstone of the standard annual physical.