







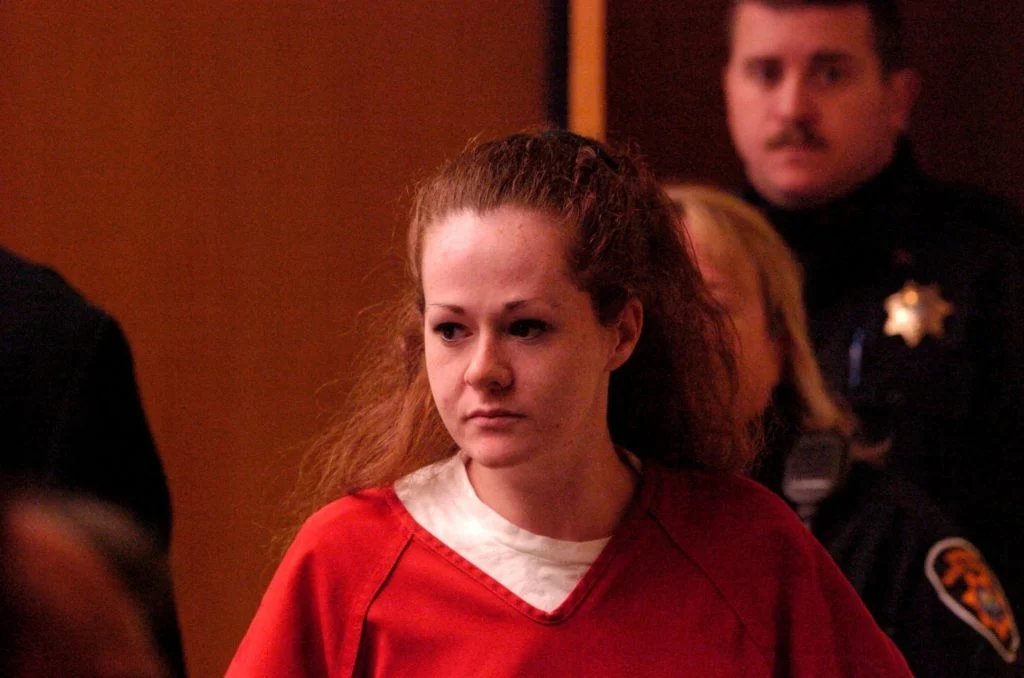
Introduction: A Procedure Gone Wrong
The Tennessee Department of Correction (TDOC) faced a harrowing crisis this past Wednesday when a scheduled lethal injection attempt on death row inmate Christa Pike resulted in a procedural failure of significant magnitude. Despite the administration of two separate doses of pentobarbital, the state’s primary execution drug, Pike did not succumb to the lethal protocol. Instead, she remains alive, currently held in critical condition under medical supervision.
This unprecedented incident has sent shockwaves through the American legal and correctional systems, reigniting the long-standing, polarized debate regarding the efficacy, constitutionality, and morality of capital punishment. As lawyers scramble to address the implications of this botched attempt, the state of Tennessee finds itself under intense scrutiny, facing questions about medical oversight, the integrity of its drug supply, and the potential violation of the Eighth Amendment, which prohibits cruel and unusual punishment.
The Case of Christa Pike: A Violent History
To understand the gravity of the current situation, one must look at the path that led Christa Pike to death row. In 1995, at the age of 18, Pike was convicted of the brutal torture-murder of Colleen Slemmer, a 19-year-old classmate at the Knoxville Job Corps Center.
The details of the crime, which emerged during the subsequent trial, were described by prosecutors as exceptionally heinous. Pike, along with an accomplice, lured Slemmer to a remote wooded area under the pretense of a truce. Once there, the victim was subjected to a sustained and gruesome assault, which concluded with her murder. Pike was subsequently sentenced to death, becoming one of the youngest women in the United States to receive such a sentence. Over the last three decades, her case has moved through the appellate process, eventually resulting in the execution order that was carried out—unsuccessfully—this week.
Chronology of the Failed Execution
The events of Wednesday unfolded in a manner that has left experts in constitutional law and forensic medicine baffled. According to reports from legal representatives, the execution process began as scheduled.
- The Preparation: State officials followed the standard operating procedure, moving Pike to the execution chamber.
- The First Dose: The initial administration of pentobarbital was intended to induce rapid unconsciousness and respiratory failure. However, monitors indicated that the drug failed to produce the desired physiological effect.
- The Second Dose: Following protocol for a delayed response, officials administered a second, supplementary dose.
- The Aftermath: Despite the double dosage, Pike remained conscious. The execution team was forced to halt the procedure, and she was subsequently transported to a medical facility.
Attorneys for Pike have characterized the event as a "torturous failure," arguing that the inmate was subjected to significant physical distress while the state attempted to end her life. The fact that the procedure was aborted after the second dose suggests a critical breakdown in either the chemical potency of the drugs or the administration process itself.
Expert Analysis: A Conversation on Execution Protocols
In the wake of the incident, PBS NewsHour’s Amna Nawaz sat down with Deborah Denno, a professor at the Fordham School of Law and a leading expert on lethal injection protocols. The discussion centered on the mechanical and legal failures inherent in modern execution methods.
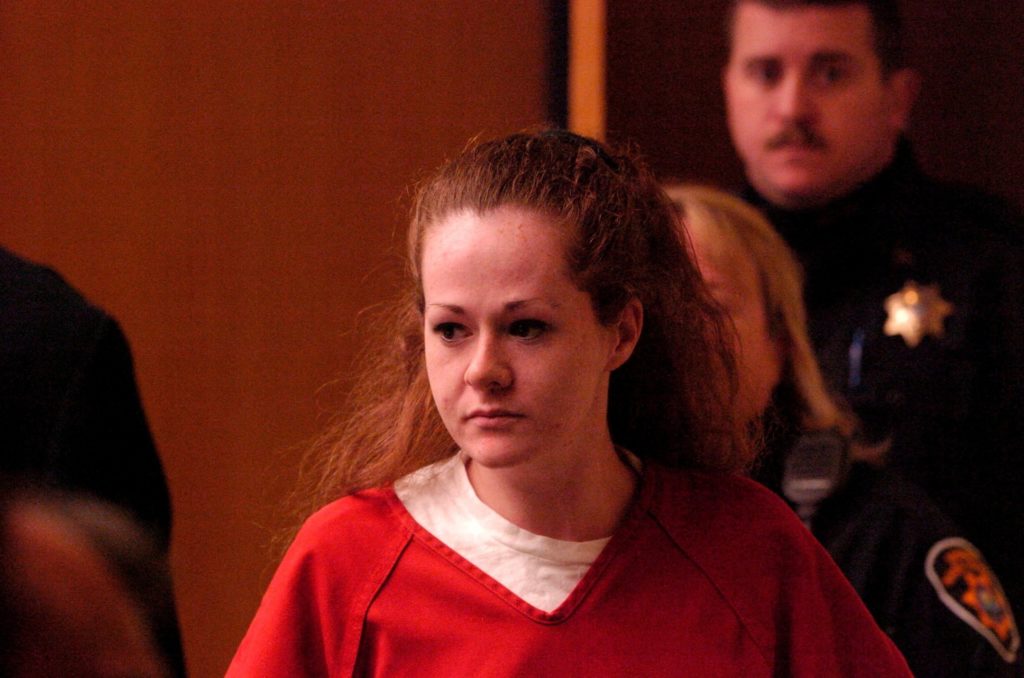
Denno noted that the shift toward pentobarbital—often used because of the difficulty states have in sourcing traditional three-drug cocktails—has not necessarily led to more reliable outcomes. "We are seeing a trend where states are operating in a shroud of secrecy," Denno stated. "When they cannot procure standardized pharmaceuticals, they often rely on compounding pharmacies or untested supplies. This, inevitably, leads to botched procedures."
The conversation highlighted the "cruel and unusual" threshold. If an inmate is conscious during the administration of a drug meant to paralyze or stop the heart, they may experience agony that cannot be communicated. This, Denno argued, is the primary fear of the Supreme Court’s jurisprudence regarding the death penalty.
Official Responses and Administrative Silence
The Tennessee Department of Correction has been notably reticent in the hours following the incident. In a brief, carefully worded statement, a spokesperson for the department confirmed that an "execution procedure was halted" and that the inmate is currently receiving medical care.
However, the lack of transparency has drawn sharp criticism from civil rights organizations. The American Civil Liberties Union (ACLU) of Tennessee issued a statement calling for an immediate, independent investigation into the state’s execution protocols. "The public deserves to know how the state of Tennessee managed to fail at the most final of its responsibilities," the statement read. "This is not just a medical error; it is a systemic failure of justice."
Governor Bill Lee’s office has yet to issue a formal comment, though it is expected that the state will eventually commission an internal review. Historically, states that have experienced botched executions often implement temporary moratoriums while they revise their "execution manuals," though these revisions rarely address the core issues of drug supply and medical oversight.
Supporting Data: The Pattern of Botched Executions
This incident is not an isolated event. According to data compiled by the Death Penalty Information Center (DPIC), the frequency of "botched" executions has risen in the last decade. A botched execution is generally defined as one that deviates from the planned protocol, resulting in prolonged suffering or an unexpected failure to kill the inmate.
- Pharmaceutical Shortages: Since European manufacturers stopped selling drugs to U.S. prisons for use in executions, states have been forced to source drugs from secondary, less-regulated markets.
- Medical Professional Involvement: The American Medical Association (AMA) strictly forbids physicians from participating in executions. This leaves the task to prison staff who lack the medical training to ensure IV placement or drug efficacy, increasing the likelihood of complications.
- The "Pentobarbital Crisis": As seen in Pike’s case, even when states obtain the desired drug, the lack of oversight on shelf life and chemical purity poses a significant risk of failure.
Statistical analysis shows that since 2010, at least 15% of all lethal injection attempts in the U.S. have been classified as "problematic" or "botched."

Implications for the Future of Capital Punishment
The failed execution of Christa Pike raises profound questions about the viability of the death penalty in Tennessee and across the nation.
Legal Challenges
Defense attorneys across the country are expected to use this incident to challenge existing execution protocols in their own jurisdictions. If the state cannot ensure a "painless" execution—a standard established in Baze v. Rees—then the entire process may be deemed unconstitutional. We are likely to see a surge in "as-applied" challenges, where inmates argue that the specific drugs and methods used by their state pose an "objectively intolerable risk of harm."
Ethical and Moral Considerations
For opponents of the death penalty, the incident provides fresh evidence that the state is fundamentally incapable of performing executions in a humane manner. The spectacle of a failed execution serves as a grim reminder that when the government assumes the role of executioner, the margin for error is nonexistent.
For proponents, the failure is seen as a technical glitch rather than a moral one. They argue that the focus should remain on the heinous nature of the crimes committed by death row inmates, and that the state should simply move to "more reliable" methods, such as nitrogen hypoxia or firing squads, if lethal injection proves unreliable.
The Impact on the Victim’s Family
Perhaps the most overlooked victims in this scenario are the families of those who were murdered by the inmates. For the family of Colleen Slemmer, the prospect of closure has been shattered by the state’s failure. The legal limbo created by a botched execution forces families to relive their trauma indefinitely, as the case becomes a matter of constitutional debate rather than a finalized sentence.
Conclusion: A System in Disarray
The case of Christa Pike will undoubtedly serve as a watershed moment in the history of capital punishment in Tennessee. As the state grapples with the fallout, the broader American public is forced to confront the grim realities of the machinery of death. Whether this leads to a permanent moratorium, a shift toward alternative methods, or a renewed push for transparency remains to be seen.
One thing is certain: the failure to execute Christa Pike has exposed the fragile, often opaque, and increasingly dangerous nature of state-sanctioned death. The legal, ethical, and medical questions raised this week will linger in the courts and the public consciousness for years to come, further complicating the already precarious standing of the death penalty in a modern, democratic society.