







In the landscape of modern medicine, the mantra "more is better" has increasingly come under fire. Nowhere is this more evident than in the field of orthopedics, where a new, comprehensive analysis of Medicare data has exposed a startling reality: the likelihood of a veteran receiving a "low-value" orthopedic procedure is often determined less by their clinical symptoms and more by their zip code.
The study, led by Dr. Samantha Auty and her colleagues at Boston University, provides a granular look at how medical practice patterns—often driven by local clinical traditions or the influence of specific providers—result in massive, unexplained geographic variations in healthcare delivery.
Main Facts: The "Low-Value" Crisis
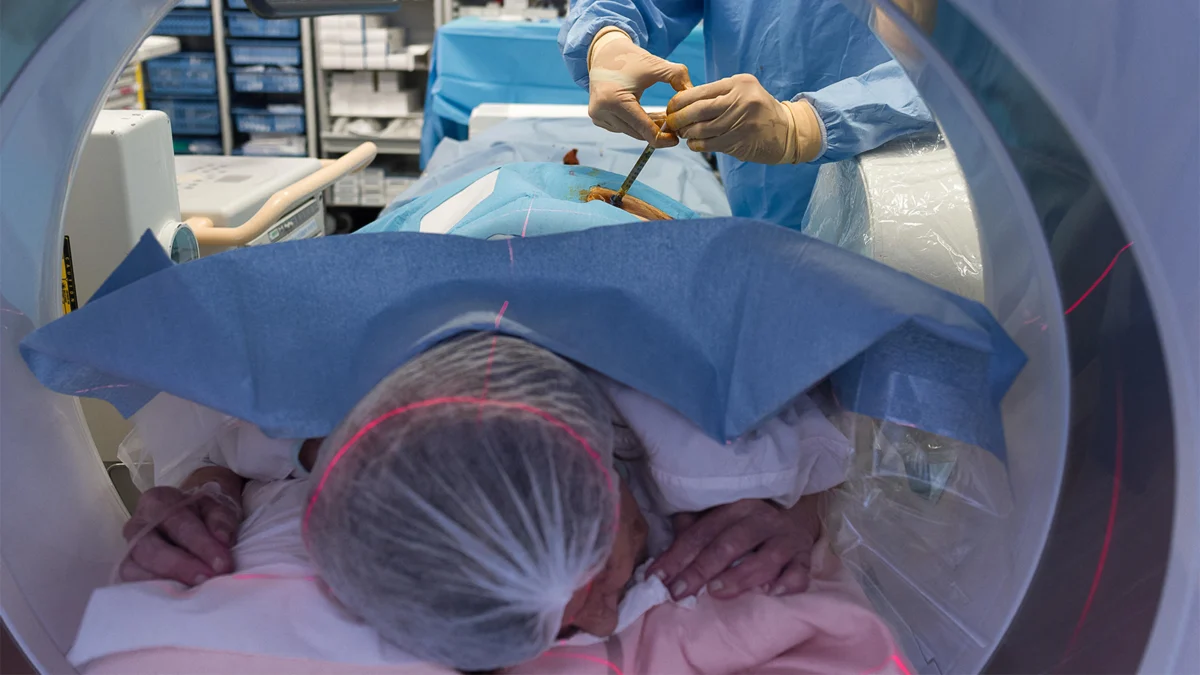
The term "low-value service" (LVS) refers to medical procedures where the clinical benefits are outweighed by the potential risks and financial costs. In the context of the study published in JAMA Network Open, researchers scrutinized five specific orthopedic procedures: vertebroplasty, spinal fusion, spinal injections, advanced spinal imaging (such as MRIs for uncomplicated pain), and knee arthroscopy.
These procedures were categorized as "low-value" only when they failed to meet established clinical guidelines. For instance, while a vertebroplasty can be a life-changing intervention for a patient with an unhealed, painful vertebral fracture, it is considered low-value when performed on patients whose fractures are asymptomatic or when conservative measures—such as rest and pain management—have not been adequately exhausted.
The study’s most alarming finding is the sheer scale of the disparity. In some hospital referral regions, the rate of these low-value services reached as high as 72 per 100 persons. In others, the same procedures were performed on almost no one. This is not a matter of minor statistical variance; it is a fundamental shift in the standard of care based on regional geography.
Chronology: A Decade of "Less Is More"
The medical community’s awakening to the dangers of over-treatment did not happen overnight. The movement to curtail unnecessary care gained significant momentum around 2010.
- 2010: The "Less Is More" movement began to gain traction in medical literature, arguing that for many diagnostic tests and surgical interventions, the harms—including radiation exposure, surgical complications, and financial burden—far outweighed the clinical gain.
- 2012: The American Board of Internal Medicine launched the "Choosing Wisely" campaign. This landmark initiative encouraged professional societies to create lists of "five things physicians and patients should question," aimed at eliminating waste and harm.
- 2017–2022: The study period for the current research. By analyzing Medicare fee-for-service claims for veterans aged 65 and older, Dr. Auty and her team sought to bridge the gap between national guidelines and real-world implementation.
- 2024: Publication of the JAMA Network Open findings, which serves as a definitive update on how far the medical community still has to go in reducing systemic over-treatment.
Supporting Data: Mapping the Disconnect
To understand the depth of the issue, the researchers mapped the 306 hospital referral regions defined by Medicare. They found that the 75th percentile of "very high" usage regions dwarfed the 75th percentile of "very low" usage regions.
The Myth of Regional Trends
One of the most counterintuitive findings was the lack of correlation between different types of low-value services. One might assume that a region prone to over-treating spinal issues would also be prone to over-treating knee issues. However, the data suggested otherwise. The correlation coefficients among the service types ranged from -0.25 to 0.22.
This indicates that regional variation is not driven by a singular "culture of over-treatment" within a hospital system, but rather by procedure-specific factors. A hospital might be an outlier for aggressive spinal injections but perfectly aligned with national standards for knee arthroscopy. This "siloed" behavior suggests that the drivers of low-value care are likely tied to the specific influence of local surgeons, hospital culture, or reimbursement incentives specific to a single department.
Addressing Visual Distortion
The study also provided a cautionary note on data visualization. The maps used to illustrate these findings—which relied on geographic regions—can be misleading. Because western hospital referral regions cover vast, sparsely populated landmasses, they dominate the visual field, while densely populated East Coast regions appear as tiny, invisible dots. Researchers noted that these cartographic distortions, combined with the limitations of Mercator projections, often obscure the fact that the highest rates of over-treatment are often occurring in densely populated areas.
Official Responses and Clinical Implications
The implications of these findings are profound for both policy and patient safety. Because there is no "universal" culprit driving all low-value care, a blanket policy response is unlikely to be effective.
"These findings may inform procedure-specific strategies for reducing orthopedic LVS," the authors noted. The team suggests that interventions should be highly targeted. For example, a hospital system with a high rate of unnecessary spinal imaging might implement a prior authorization program specifically for that diagnostic tool, while a region over-performing knee arthroscopy might benefit from network designs that steer patients toward conservative physical therapy first.
The Challenge of Chronic Pain
The study highlights the difficulty of managing chronic musculoskeletal pain. In many cases, the root cause of pain is difficult to diagnose via advanced imaging. Patients, desperate for relief, often push for surgery, and surgeons, influenced by local traditions or pressure to "do something," may feel compelled to operate even when evidence suggests the procedure will fail. The study emphasizes that "patient selection is key." Without strict adherence to clinical pathways, the path of least resistance is often the most expensive and least effective one.
Implications for Future Policy
While this study provides a roadmap for where to look, it also highlights significant gaps in our current understanding.
- The Gender Gap: A major limitation of this research is that the cohort consisted almost entirely of veterans, who are predominantly male. Consequently, these findings may not fully represent the patterns of care seen in the broader population, particularly regarding procedures like knee arthroscopy, which may be influenced by different demographic variables.
- Spending vs. Outcomes: The study did not explicitly link the volume of low-value services to total healthcare spending or long-term clinical outcomes. Future research must determine if these high-rate regions are not only wasting money but also harming patients through avoidable surgical complications.
- Targeted Policy: The researchers advocate for a shift away from broad, national mandates toward localized, procedure-specific interventions. By identifying the "hotspots" for specific low-value services, health systems can better deploy resources, such as mandatory second opinions or increased education on conservative pain management.
Conclusion: A Call to Action
The data provided by Dr. Auty’s team serves as a wake-up call for the healthcare system. When the standard of care is dictated by geography rather than evidence, the result is an inequitable system that exposes patients to unnecessary risk. The "Less Is More" movement has spent over a decade building the foundation of evidence; the next decade must be defined by the rigorous implementation of these findings. By focusing on procedure-specific strategies and challenging the local traditions that favor surgery over conservative care, the medical community can move toward a more efficient, patient-centered future.