









For decades, the standard medical advice for aging adults has been as predictable as it is ubiquitous: "Take your calcium and vitamin D." From the medicine cabinets of retirees to the clinical guidelines of major health organizations, these supplements have been heralded as the frontline defense against the silent epidemic of bone fragility. However, a landmark, large-scale review published in The BMJ has shattered this long-standing convention, suggesting that for the vast majority of older individuals, these daily pills offer little to no meaningful protection against the falls and fractures that threaten their independence.
The Gravity of the Problem: Why Falls Matter
To understand the significance of this research, one must first appreciate the scale of the crisis. As the global population ages, falls have emerged as a primary public health concern. Statistical data paints a sobering picture: nearly one in three adults aged 65 and older experiences at least one fall annually.
For an older person, a fall is rarely a trivial event. It is often the catalyst for a cascade of negative health outcomes, including complex fractures, chronic debilitating pain, and a sudden, precipitous decline in mobility. Beyond the physical trauma, the psychological toll—often manifesting as a paralyzing fear of falling again—frequently leads to social isolation, a reduced quality of life, and in many instances, an irreversible move into long-term residential care. Given these stakes, finding robust, evidence-based methods to prevent bone degradation and physical instability is not just a clinical preference; it is a fundamental public health imperative.
The Conventional Wisdom: A History of Assumptions
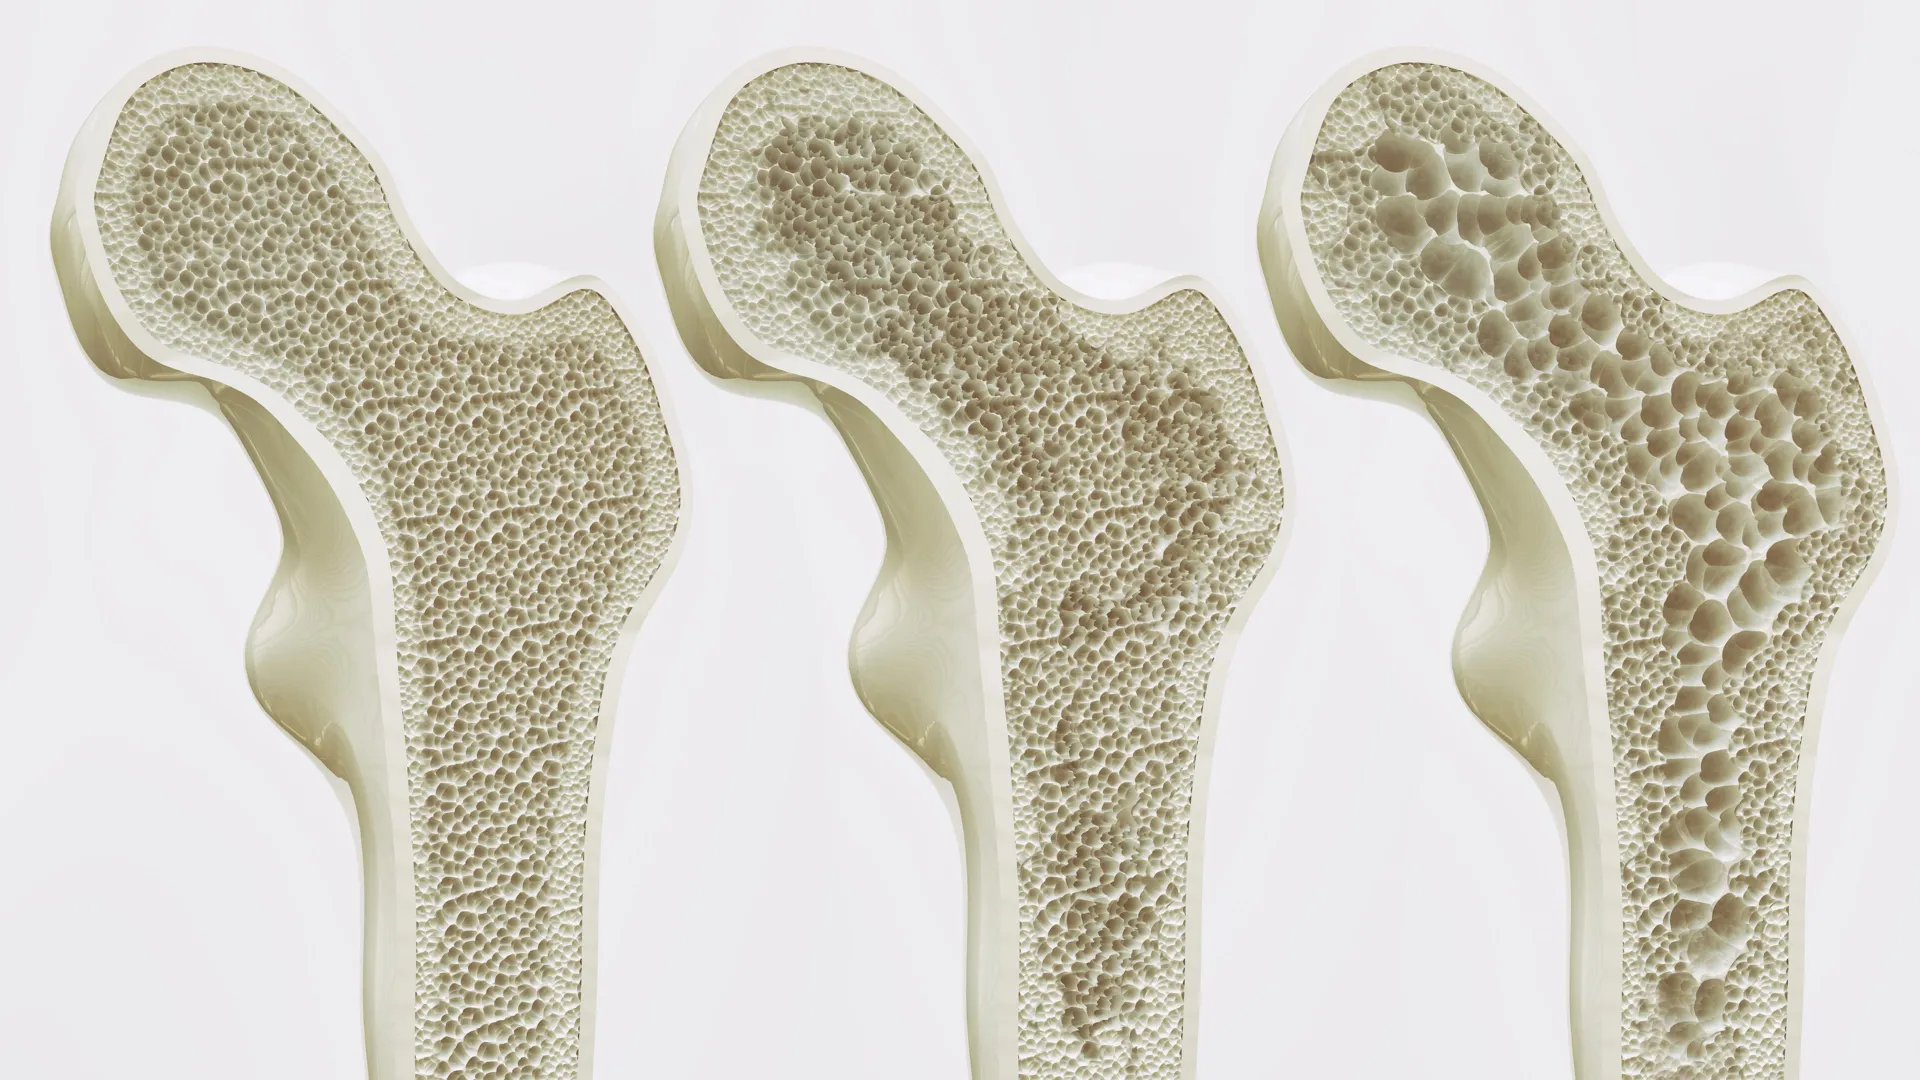
Calcium and vitamin D have been synonymous with skeletal integrity for generations. Biologically, the logic seems impeccable: calcium is the essential structural "brick" of the skeleton, and vitamin D acts as the critical "mortar," facilitating the absorption of calcium and regulating bone metabolism.
However, the scientific community has harbored doubts for years. While the biological mechanism is sound, clinical outcomes have often failed to mirror theoretical expectations. Previous meta-analyses have frequently shown that calcium or vitamin D, when administered in isolation, do little to alter fracture risk. Even when combined, the results have been inconsistently encouraging, leading to a state of perpetual uncertainty regarding their efficacy in preventing falls.
Despite this lack of definitive proof, the practice of routine supplementation has continued to accelerate. Prescriptions for vitamin D have risen substantially over the last decade, bolstered by clinical guidelines and recommendations from regulatory agencies that, until now, have prioritized traditional physiological models over rigorous longitudinal data.
A Massive Undertaking: The Methodology of the Review
To settle the debate, researchers based in Canada conducted a massive, comprehensive review of the available evidence. Their work involved an analysis of 69 randomized controlled trials (RCTs) encompassing a staggering 153,902 participants.
In the world of medical research, the randomized controlled trial is the "gold standard." By randomly assigning participants to either a treatment group or a placebo/no-treatment group, researchers can isolate the specific effect of the supplement while minimizing the "noise" created by lifestyle, socioeconomic, or environmental variables. The research team assessed the risk of bias across these studies using established, rigorous Cochrane-style methods to ensure that their conclusions were based on the most reliable data available.
The Verdict: Evidence of Absence
The researchers set clear, pre-defined thresholds for what would constitute a "clinically meaningful benefit." After synthesizing the data from the 69 trials, the conclusion was stark: there was little to no evidence that these supplements provide a significant reduction in the risk of fracture.
Breakdown of the Findings:
- Calcium Supplements: Based on moderate-certainty evidence from 11 trials involving 9,067 participants, calcium alone failed to provide meaningful protection against fractures.
- Vitamin D Supplements: Utilizing high-certainty evidence from 36 trials involving 92,045 participants, the researchers found that vitamin D failed to reduce fracture risk or fall incidence.
- Combined Supplementation: Perhaps most notably, high-certainty evidence from 15 trials involving 51,126 participants showed that taking both calcium and vitamin D together—a common practice in nursing homes and geriatric care—was equally ineffective in preventing fractures or falls.
The researchers scrutinized these results across specific outcomes, including hip fractures and falls, yet the pattern remained consistent: the supplements failed to demonstrate a meaningful impact on skeletal health or physical stability.
Important Nuances and Exceptions
While the results are compelling, the researchers are careful to note that they are not universal. The analysis identified that for specific subsets of the population—such as those with diagnosed metabolic bone disorders, individuals with severe nutritional deficiencies, or patients already undergoing specialized osteoporosis treatment—the findings may not apply. These patients remain under the care of specialists, and the study does not suggest they should abandon their prescribed regimens without consulting a physician.
Furthermore, the team tested the consistency of their results against a variety of factors, including the age and sex of participants, their history of previous fractures or falls, and their baseline dietary calcium intake. The lack of variation in the findings across these subgroups reinforces the validity of the study’s primary conclusion: for the general older population, the "routine" approach to supplementation is largely ineffective.
The Call for a Policy Shift
The authors of the BMJ review did not mince words. Their analysis leads to an inescapable conclusion: current clinical and regulatory guidelines, which often advocate for the mass distribution of calcium and vitamin D, are not supported by the existing evidence.
"The evidence does not support routine supplementation," the authors wrote. They have formally called for clinical guideline panels and regulatory agencies to re-evaluate their recommendations. In medicine, "first, do no harm" is a core tenet, but a corollary to this is the efficient use of healthcare resources. Millions of dollars are spent annually on supplements that, according to this data, provide no tangible health benefit for the average older adult.
Beyond the Pill: Rethinking Fall Prevention
If supplements are not the answer, what is? A linked editorial published alongside the study argues that it is time to pivot. For too long, the medical establishment has focused on a "pharmacological fix"—the idea that a vitamin or mineral could solve the complex, multifactorial problem of aging.
Instead, the editorial authors propose a shift toward interventions that have demonstrated proven, meaningful outcomes:
- Balance Training: Improving proprioception and stability is critical for preventing the initial fall.
- Resistance Exercise: Building muscle mass and skeletal strength through targeted physical activity is vastly more effective than supplementation for maintaining functional independence.
- Multifaceted Programs: These include environmental audits (e.g., removing tripping hazards in the home), medication reviews (to check for drugs that cause dizziness), and personalized physical therapy.
Implications for the Future
The BMJ study serves as a wake-up call for both patients and clinicians. It highlights a common trap in modern medicine: the tendency to rely on the idea of a solution rather than the proof of one.
For the older adult, this news should not be viewed as a signal to abandon all concern for bone health, but rather as an invitation to focus on what truly works. Health is not found in a bottle of supplements; it is found in the daily habits that foster strength, balance, and resilience.
As we look toward the future of geriatric care, the message is clear: preventing the next fracture will require less reliance on chemistry and more investment in physical movement. By shifting our resources toward exercise-based interventions and evidence-based fall prevention strategies, we can offer older adults something much more valuable than a daily pill: the confidence of a stable, independent life.