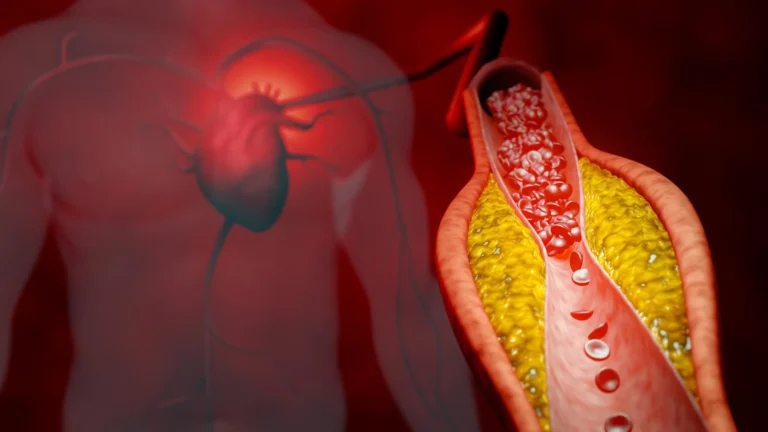








For more than 40 years, the routine prescription of beta blockers following a heart attack has been as predictable as the sun rising. For millions of patients worldwide, these medications—designed to slow the heart rate and reduce the workload on the cardiac muscle—have been the cornerstone of post-myocardial infarction (MI) care. They were the "gold standard," a non-negotiable component of the discharge packet, regardless of the severity of the heart attack or the patient’s residual heart function.
However, a paradigm shift is underway. A landmark 2025 clinical trial, the REBOOT study, has produced findings that challenge this long-standing dogma, suggesting that for a vast cohort of patients—those with uncomplicated heart attacks and preserved cardiac function—the routine use of beta blockers may be an unnecessary burden rather than a life-saving necessity.
The Evolution of Cardiac Care: A 40-Year Standard Challenged
To understand why this change is so seismic, one must look at the historical context. When beta blockers were first integrated into post-MI protocols, the landscape of cardiology was fundamentally different. In the early era of their adoption, thrombolytic therapy and primary percutaneous coronary intervention (PCI)—the rapid opening of blocked arteries—were not the standard of care. Patients often suffered more extensive heart damage, leaving them at a much higher risk for arrhythmias and sudden cardiac death. In that environment, the physiological protection offered by beta blockers was invaluable.
Today, however, the medical landscape has been transformed. Patients arriving at the hospital with a heart attack are now treated with rapid revascularization, potent statins, and advanced antiplatelet therapies. These modern interventions have drastically lowered the risk of the very complications that beta blockers were originally meant to prevent. This raises a critical, evidence-based question: If modern medicine is already effectively protecting the heart from the brink of failure, are we over-prescribing medications that carry their own set of physiological costs?
Chronology of the REBOOT Trial and Emerging Evidence
The REBOOT (REassessment of B-blocker use after myocardial infarction) trial was designed to provide a definitive answer to this question. Led by senior investigator Valentin Fuster, MD, PhD, President of Mount Sinai Fuster Heart Hospital and General Director of the Centro Nacional de Investigaciones Cardiovasculares (CNIC) in Spain, the study represented a massive undertaking in clinical research.
The Trial Design
Researchers enrolled 8,505 patients across 109 clinical centers in Italy and Spain. The study was uniquely rigorous, randomized, and conducted without pharmaceutical industry funding, ensuring that the results remained untainted by commercial bias. Participants were randomly assigned to either continue with the standard-of-care, which included beta blockers, or to avoid them, while maintaining all other essential treatments. The median follow-up period spanned nearly four years, allowing for a long-term assessment of mortality, repeat heart attacks, and heart failure-related hospitalizations.
The "Hot Line" Revelation
The results were presented during a high-profile "Hot Line" session at the 2025 European Society of Cardiology Congress in Madrid and subsequently published in The New England Journal of Medicine. The data was striking: in patients whose heart function remained preserved after a heart attack, the use of beta blockers provided no significant reduction in the risk of death, subsequent heart attacks, or hospitalizations for heart failure.
This finding did not emerge in a vacuum. It follows a trajectory of recent clinical skepticism. In 2024, the REDUCE-AMI trial reported similar findings, observing no significant mortality benefit for the same patient demographic. Conversely, other trials, such as the BETAMI-DANBLOCK studies, initially suggested some benefits, leading to a period of clinical confusion. However, a subsequent meta-analysis of individual patient data has since reconciled these findings: the benefit of beta blockers is highly dependent on the patient’s left ventricular ejection fraction (LVEF).
Supporting Data: The Nuance of Cardiac Function
The emerging consensus, fueled by the REBOOT data and supported by meta-analyses, provides a clear, data-driven framework for future prescribing habits.
- Preserved Heart Function (LVEF ≥ 50%): The evidence is now robust that for patients with normal or near-normal heart pumping ability, the routine use of beta blockers does not offer a clinical advantage.
- Mildly Reduced Heart Function (LVEF 40-49%): There is evidence to suggest that this specific group may still derive a protective, therapeutic benefit from beta blocker therapy.
- Significantly Reduced Heart Function (LVEF < 40%): For these patients, the role of beta blockers remains firmly established as a life-saving intervention.
The crucial takeaway is the move away from a "one-size-fits-all" approach. The data suggests that clinicians must now pivot toward personalized medicine, where the prescription of beta blockers is tied directly to the patient’s specific cardiac health profile rather than a generic post-MI protocol.
A Concerning Signal: The Gender Divide
One of the most sobering aspects of the REBOOT research was the discovery of a sex-specific disparity. A substudy published in the European Heart Journal revealed that women who received beta blockers experienced a higher risk of adverse outcomes—including death, recurrent heart attack, or heart failure hospitalization—compared to women who did not receive them.
This increased risk was particularly pronounced in women with completely normal heart function (LVEF 50% or higher). In this group, the absolute risk of mortality was 2.7 percent higher in the treated group compared to the untreated group over a 3.7-year follow-up. This unexpected signal has sparked a major conversation within the cardiology community about the need to better understand how cardiovascular medications interact with sex-specific biology. While researchers caution that these findings are observational and do not imply that women should unilaterally stop their medication, it underscores the danger of applying findings derived from male-dominated historical trials to female patient populations.
Official Responses and the Future of Clinical Guidelines
The investigators behind the REBOOT trial are confident that their findings will be the catalyst for a global update to clinical practice guidelines.
"This trial will reshape all international clinical guidelines," says Dr. Valentin Fuster. "It joins other previous landmark trials led by CNIC and Mount Sinai that have already transformed some global approaches to cardiovascular disease."
Dr. Borja Ibáñez, the study’s Principal Investigator and Scientific Director of the CNIC, emphasized the practical necessity of this shift. "Currently, more than 80 percent of patients with uncomplicated myocardial infarction are discharged on beta blockers. The REBOOT findings represent one of the most significant advances in heart attack treatment in decades," he noted.
Dr. Ibáñez pointed out that by eliminating unnecessary medication, doctors can effectively reduce the pill burden for patients. "After a heart attack, patients are typically prescribed multiple medications, which can make adherence difficult," he explains. "If we can remove an unhelpful medication, we not only limit side effects like fatigue, bradycardia, and sexual dysfunction, but we also simplify the recovery regimen, ultimately improving the patient’s quality of life."
Implications: The Move Toward Personalized Heart Care
The implications of the REBOOT trial extend far beyond the prescription of a single class of drugs. They signal a maturing of cardiovascular medicine—a transition from a defensive, reactive posture to a more surgical, data-driven approach.
Reducing the Pill Burden
Polypharmacy—the use of multiple medications—is a significant barrier to recovery. Patients who are overwhelmed by their drug regimens are less likely to adhere to any of them. By streamlining treatment to include only those drugs that provide a proven, measurable benefit, the healthcare system can foster better compliance with other essential, life-saving therapies like statins and antiplatelet drugs.
Improving Quality of Life
Beta blockers are notorious for side effects that, while not always life-threatening, can significantly diminish a patient’s daily experience. Fatigue, lethargy, and sexual dysfunction are common complaints that often go unaddressed in the rush to ensure the heart is "protected." If a patient with a clean bill of cardiac health can avoid these side effects without sacrificing their long-term survival, it represents a substantial win for modern medicine.
A Call for Rigorous Self-Examination
Perhaps the most profound implication of the REBOOT trial is the precedent it sets for the medical establishment. Medicine often struggles to "unlearn" standard practices. Once a drug is established as a standard, it often remains so for decades, fueled by institutional inertia rather than updated science. REBOOT serves as a model for how the medical community can—and should—rigorously challenge the necessity of older treatments in the light of newer, more effective diagnostic and therapeutic technologies.
Conclusion
The findings from the REBOOT trial do not signal the death of the beta blocker. For millions of patients with compromised cardiac function, these drugs remain a vital tool in the cardiologist’s arsenal. However, the trial has effectively ended the era of the indiscriminate, routine prescription of beta blockers for all heart attack survivors.
For the vast majority of patients who suffer an uncomplicated myocardial infarction and retain good heart function, the future of recovery is likely to be simpler, less burdened by unnecessary chemicals, and more precisely tailored to their individual physiology. As clinical guidelines begin to reflect these findings, the healthcare community moves one step closer to a model of care that prioritizes both the longevity of the patient and the quality of their daily life. This is not just an update to a prescription protocol; it is a fundamental advancement in how we define and deliver post-heart attack recovery.