









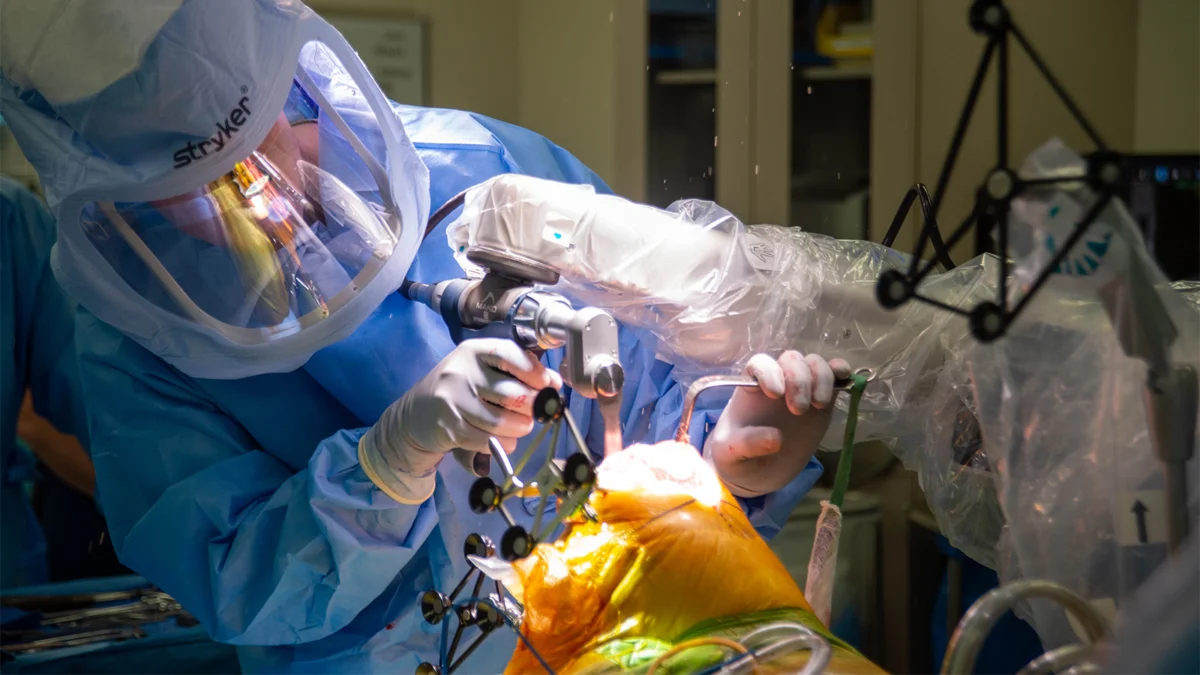
In the rapidly evolving landscape of orthopedic surgery, the integration of robotics has been heralded as a "technological revolution." Proponents argue that robotic-assisted arthroplasty offers a level of surgical precision that the human hand simply cannot replicate. However, a massive, comprehensive analysis of over 2.5 million surgical procedures in the United Kingdom has cast a significant shadow over these claims. The study, published in The BMJ, suggests that for all the investment in high-end machinery, robotic-assisted knee and hip replacements offer no tangible clinical benefit over conventional, manual surgical techniques.
The Core Findings: A Question of Value
The research, led by Hasan R. Mohammad, MRCS, DPhil, MRes, of Queen Mary University in London, analyzed data from the National Joint Registry (NJR) covering England, Wales, Northern Ireland, the Isle of Man, Guernsey, and Jersey. The investigation scrutinized the outcomes of total and unicompartmental knee replacements and hip arthroplasties performed between 2018 and 2024.
The data yielded a startling conclusion: revision rates—the gold standard for measuring the failure of an implant—were nearly identical between the robotic-assisted groups and those who underwent standard manual surgery. Over a five-year postoperative window, the survival rate of these implants showed no statistically significant divergence.
The implications for healthcare spending are profound. Each robotic surgical system carries an acquisition price tag of approximately £1 million ($1.3 million), compounded by additional per-procedure costs ranging from £1,000 to £2,500 ($1,300 to $3,300). When viewed through the lens of patient outcomes, the researchers suggest that the significant capital and operational expenditure required for robotic integration may constitute a misuse of public funds, particularly within the resource-constrained environment of the National Health Service (NHS).
Chronology: The Rise of Robotic Orthopedics
The enthusiasm for robotic surgery in the U.K. did not emerge in a vacuum. For years, the orthopedic industry has marketed robotic platforms as the solution to "malalignment"—the misalignment of implants that is a known precursor to joint loosening and premature revision.
- 2018–2020: Early adoption of robotic platforms gains momentum in private and select NHS hospitals, fueled by promises of faster recovery times and higher precision.
- 2023: The U.K. government begins formalizing plans to modernize surgical infrastructure, identifying robotics as a key pillar for efficiency.
- July 2024: The British government releases its "10-Year Health Plan for England," explicitly outlining a goal to increase the use of robotic-assisted hip and knee arthroplasties sevenfold.
- Late 2024: The findings from the Mohammad et al. study arrive, creating a potential policy roadblock for the government’s ambitious expansion plans.
This chronology highlights a growing tension between technological ambition and empirical evidence. While the NHS has been tasked with embracing innovation, the recent findings provide a sobering check on the pace at which these technologies should be integrated into standard practice.
Supporting Data: Robust Methodology
The strength of the Mohammad study lies in its scale. By analyzing 2.5 million procedures, the researchers were able to employ a "target trial emulation" analysis, which mimics the structure of a randomized clinical trial using observational registry data.
To ensure parity, the researchers propensity-matched patients undergoing robotic surgery with those who received conventional care. The matching criteria were rigorous, accounting for clinical and demographic parameters, including the surgeon’s annual procedure volume, which is a known variable in surgical success.
- Total Hip Replacement (THR) Cohorts: Patients had an average age of 66, with 56% being women. Over 90% of surgeries were indicated for osteoarthritis.
- Total Knee Replacement (TKR) Cohorts: Patients averaged 70 years of age, with 56% female.
- Unicompartmental Knee Replacement (UKR) Cohorts: Patients averaged 66 years of age, with 54% female.
The resulting 5-year implant survival rates were virtually indistinguishable across all categories. In the THR cohort, 98.6% of manual surgeries survived versus 98.8% of robotic surgeries. When comparing the broader, unmatched populations, the results remained similarly consistent. Furthermore, when examining all-cause mortality among THR patients, the team found no significant differences, effectively debunking the notion that robotic assistance provides a survival or systemic safety advantage.
Nuance and Minor Observations
While the primary endpoint—revision rate—remained unaffected, the study did note some minor variances. In the unmatched analysis, THR revisions for dislocation were lower in the robotic group (0.11% vs 0.33%), as were incidents of fractures. However, once the cohorts were propensity-matched to account for surgeon experience and patient baseline health, these differences vanished, becoming statistically insignificant.
The researchers acknowledge that revision rates are a "hard" endpoint and that other, "softer" metrics—such as patient-reported pain levels, stiffness, or overall joint function—were not the primary focus of this specific registry-based analysis. It remains possible that robotic surgery improves the patient’s subjective experience or recovery speed in the months immediately following surgery, even if those benefits do not translate into longer-term hardware stability.
Official Responses and Regulatory Implications
The findings place the National Institute for Health and Care Excellence (NICE) in a difficult position. NICE is the regulatory body responsible for determining which medical technologies represent a justifiable expenditure of NHS resources. Given that NICE guidelines prioritize both clinical efficacy and cost-effectiveness, the current study provides a strong argument against the widespread, state-funded rollout of robotic platforms.
If NICE adopts a conservative stance, it could effectively stall the government’s 10-year plan. The document published by the government this past July explicitly stated, "Beginning next year, we will expand surgical robot adoption in line with NICE guidelines." If the "guidelines" are informed by these new data, the expansion might be limited to specific, high-risk cases rather than becoming the standard of care for the general population.
Implications: A Call for Evidence-Based Innovation
The study concludes with a note of caution regarding the generalizability of the findings. Because the research focused on the U.K. healthcare system, factors such as wait times, surgeon training, and the specific patient demographics of the NHS might not perfectly map onto the private-pay systems seen in the United States or other global markets.
Moreover, the authors admit that as an observational study, they cannot fully account for "residual confounding"—the possibility that surgeons who choose to use robots are fundamentally different from those who prefer manual techniques, or that the patients selected for robotics were already predisposed to better outcomes.
Ultimately, the study serves as a poignant reminder that in the medical field, innovation must be subservient to evidence. The "robotic revolution" in orthopedics has been driven more by the allure of precision engineering than by demonstrated patient superiority. As healthcare systems globally face mounting fiscal pressures, the burden of proof for expensive new technologies has never been higher.
For the millions of patients awaiting joint replacements, the takeaway is clear: the skill of the surgeon and the quality of the implant remain the primary determinants of a successful procedure. While the robot may be a sophisticated tool, the current data suggests it is not the panacea that will fundamentally alter the long-term success of joint replacement surgery. Surgeons, policymakers, and patients alike must now decide whether the aesthetic appeal of "robot-assisted" care is worth the staggering financial premium, or if those resources could be more effectively deployed elsewhere in the orthopedic ward.